Low Libido on TRT: 7 Causes & What to Check
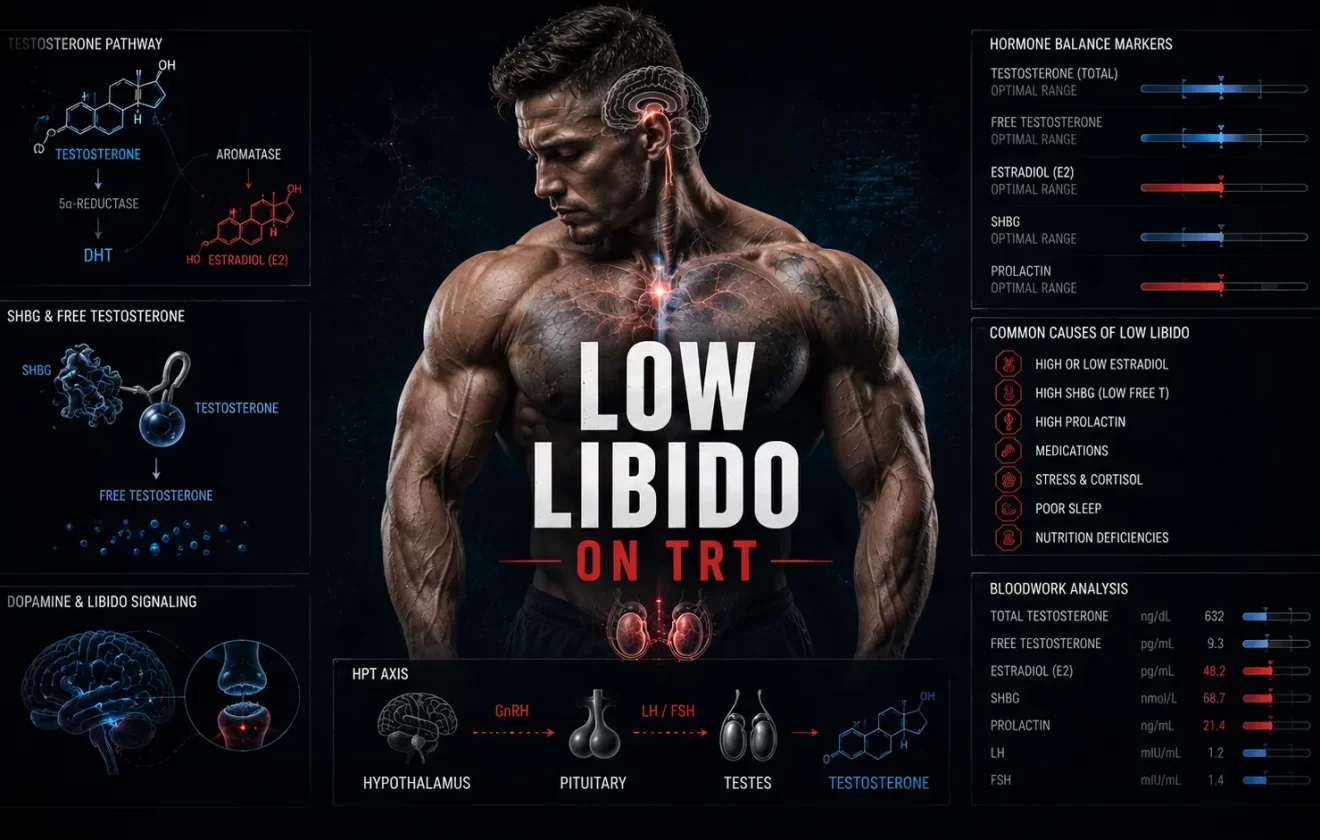
Low libido on TRT, when the numbers look fine
It is one of the most disorienting things in men's health: you start testosterone, your labs say you are "optimized," and your sex drive is still flat - or it roared back for three weeks and then vanished. Low libido on TRT is common, and it almost never means you need a bigger dose. Usually the problem is estradiol that is too high or crashed too low, low free testosterone hiding behind a normal total, high prolactin, a medication, or the simple fact that testosterone sets the stage for desire but does not create it. This guide troubleshoots low libido on TRT the way a good clinician would - in order, with the labs that actually matter.
Why libido can stay low on TRT
Once you are in range, extra testosterone adds little desire and can worsen estradiol, mood and hematocrit.
Both high E2 and crashed E2 (often from an aromatase inhibitor) flatten libido. Balance beats blocking.
A great total testosterone with high SHBG can still leave free testosterone - and desire - low.
The single most useful mindset shift: testosterone is permissive, not a dial you turn up for more desire. In the large Testosterone Trials, treatment did improve sexual desire and activity, but the effect was modest - real, not miraculous. So when you have low libido on TRT despite a solid testosterone level, the answer is a systematic work-up, not a dose increase.
This page is about therapeutic testosterone. It is not about high-dose steroid cycles - for the crashed drive that comes with blast-and-cruise or PCT, see libido on steroids. And if you have not started treatment and are still wondering whether low testosterone is behind your symptoms in the first place, begin with low testosterone symptoms.
Libido is not the same as erections - sort out which one is the problem
Before troubleshooting, separate two things people lump together. Libido is desire - the mental urge for sex, driven mostly by the brain. An erection is a plumbing event - blood flow driven by vascular and nerve health. They overlap but they are not the same, and the fixes differ. A man can have strong desire and unreliable erections (a vascular or performance-anxiety problem), or reliable erections and no desire at all (the classic low libido on TRT picture).
Why this matters: if your real issue is erections, the work-up runs toward cardiovascular and metabolic health, PDE5 inhibitors and blood-flow - not the desire pathway. If it is genuinely low libido on TRT, the work-up below (estradiol, free testosterone, prolactin, dopamine, medications) is the right map. And a reality check for anyone starting testosterone specifically to reignite desire: TRT is replacement, not an aphrodisiac. It restores desire that was lost to a genuine deficiency; it does not manufacture a supercharged sex drive in a man whose testosterone was never the problem, which is exactly why the Testosterone Trials found real but modest gains.
The estradiol sweet spot - and the aromatase-inhibitor trap

If there is one lever behind low libido on TRT, it is estradiol. Estrogen is not a female hormone to be minimized in men - it is essential for male sexual desire. In a landmark controlled study, when researchers suppressed estrogen in men who still had adequate testosterone, their sexual desire fell. And in men specifically on testosterone therapy, higher estradiol was associated with higher libido. That is the opposite of the folk wisdom that estrogen is the enemy.
This is why the reflexive fix - an aromatase inhibitor like anastrozole to "control estrogen" - so often backfires and is itself a leading cause of low libido on TRT. Crash your estradiol and you get flat desire, joint pain, low mood and worse erections, even with textbook testosterone. Estradiol that is genuinely high can also dull libido and cause puffiness, so the goal is a balanced level measured on a sensitive (LC-MS/MS) assay, adjusted mainly through dose and frequency rather than a blocker. If you are wrestling with this, our guide to estradiol on TRT goes deeper.
Why a great total testosterone can still leave libido low
Men fixate on total testosterone, but your tissues respond to free testosterone - the small fraction not bound to SHBG. If your SHBG is high, a total testosterone of 900 ng/dL can still leave free testosterone (and libido) low, which is exactly the "my numbers are perfect but I feel nothing" scenario. Thyroid disease, aging, leanness and very low-carb dieting can all push SHBG up.
The fix is not necessarily more testosterone; it is understanding the total versus free testosterone picture and, sometimes, adjusting how you dose so free testosterone sits where it should. Conversely, very low SHBG can blunt symptoms too. Always read total testosterone, free testosterone and SHBG together - a habit almost no one troubleshooting low libido on TRT actually follows.
Prolactin - the overlooked libido killer
Prolactin is the hormone nobody checks and it can quietly flatten desire - a real and reversible cause of low libido on TRT. Elevated prolactin suppresses sexual desire more or less independently of testosterone, so a man with perfect T and E2 can still have low libido on TRT if prolactin is high. Reviews of male sexual dysfunction consistently link hyperprolactinaemia to reduced desire, and clinic data show it in men presenting specifically with low drive.
The point is that the fix for high prolactin is not more testosterone - it is finding the cause (medications, rarely a pituitary issue) and, when appropriate, a dopamine-boosting treatment such as cabergoline, guided by your doctor. If your libido is low on TRT and has not responded to sensible estradiol and free-testosterone management, prolactin belongs on the next blood panel.
Desire runs on dopamine, not testosterone alone
Testosterone permits desire; dopamine generates the actual wanting, which is why low libido on TRT can persist even with perfect hormones. This is why men with flawless hormones can still feel nothing: chronic stress and high cortisol, poor sleep, depression and anhedonia, heavy alcohol, and constant novelty-seeking through porn or screens all blunt the dopamine signalling that libido depends on. It is also why SSRIs - which dampen dopamine and sexual response - are such a common hidden cause of low libido on TRT.
Practically, this means the treatable causes of low desire are often behavioural and psychological, not endocrine. It also explains why non-testosterone tools sometimes work when hormones do not: melanocortin agonists like PT-141, or switching an SSRI to bupropion under medical guidance. Libido is a brain state, and the brain has to be in the game.
Why libido spikes on TRT then crashes a few weeks later

A signature complaint, and a common form of low libido on TRT: "TRT was incredible for the first few weeks, then my libido died." This honeymoon-then-crash pattern is not bad luck. When you start, testosterone (and dopamine sensitivity) can surge before estradiol and androgen receptors re-equilibrate, giving an early high; as the system settles - and especially if estradiol swings or an aromatase inhibitor is added - desire can drop back or below baseline.
The other version is a weekly rhythm: a single large injection creates a mid-week peak and a late-week trough, and some men feel their libido rise and fall with it. The fix is smoother levels, not a bigger dose - many men do better splitting the weekly dose into smaller, more frequent injections or a daily preparation. Chasing the honeymoon with more testosterone usually just raises estradiol and hematocrit while libido stays flat.
DHT, finasteride, thyroid and the medication trap
A few more drivers deserve a direct look. DHT, the most potent androgen, matters for libido, so men taking finasteride or dutasteride (for hair or prostate) - or even saw palmetto - can have low libido on TRT despite good testosterone, because those drugs block testosterone's conversion to DHT. Thyroid dysfunction blunts desire and raises SHBG. And a long list of everyday medications suppress libido: SSRIs and some other antidepressants, opioids, certain blood-pressure drugs (especially beta-blockers), and more.
- Review every medication and supplement with your prescriber before assuming the problem is hormonal.
- Do not raise your testosterone dose to overpower a 5-alpha-reductase inhibitor or an SSRI - treat the actual cause.
- Screen thyroid (TSH and free T4) if libido is low and SHBG is high.
Put together, the causes of low libido on TRT are a short, checkable list - and testosterone dose is near the bottom of it.
How to troubleshoot without chasing your tail
Low libido on TRT gets solved by changing one variable at a time and giving it long enough to judge. Hormones do not turn on a dime: after any change - a different dose, a new injection frequency, stopping an aromatase inhibitor, treating high prolactin - allow roughly four to six weeks, then re-check both how you feel and the relevant labs before changing anything else. Stacking three changes at once means you will never know which one helped.
A sane order of operations is: first confirm the basics (a sensitive estradiol, free testosterone with SHBG, prolactin, thyroid, and a medication review); fix the obvious offender if there is one; smooth your dosing before you ever raise it; and only then consider adjuncts like a dopamine-targeted option, always with your prescriber. If libido on TRT has not budged after methodically working the list, that is a reason to dig into sleep, mood and relationship factors with a professional - not a reason to keep climbing the dose. Patience plus one-variable-at-a-time beats brute force every time.
Low libido on TRT: FAQ
Why is my libido still low on TRT when my testosterone is normal or high?
Can TRT actually lower or kill your sex drive?
Does high estrogen reduce libido in men on TRT - should I take an aromatase inhibitor?
How long does it take for libido to improve on TRT, and why did mine spike then crash?
Does free testosterone or SHBG matter more than total testosterone for libido?
Should I raise my testosterone dose to fix low libido?
What labs should I get if my libido is low on TRT?
Sources & further reading
The bottom line on TRT and libido
If you have low libido on TRT, resist the urge to crank your dose - low libido on TRT rarely responds to more testosterone. Read free testosterone, SHBG, sensitive estradiol, prolactin and thyroid together; review your medications; protect estradiol rather than crushing it; smooth your levels with sensible dosing; and give the dopamine side - sleep, stress, mood - the attention it deserves. Testosterone opens the door to desire, but a whole system has to walk through it. Work the list with your prescriber and your TRT bloodwork in hand.
This article is published for educational purposes only. It explains why sexual desire can stay low on testosterone replacement therapy, drawing on publicly available clinical guidelines and peer-reviewed research on testosterone, estradiol, prolactin and sexual function. Nothing here is medical advice, a treatment recommendation, or a substitute for care from a licensed clinician. MuscleScience.org does not sell, supply, prescribe, or affiliate with any testosterone product, medication, pharmacy, or clinic.
Sexual desire is influenced by hormones, medications, sleep, mood, relationships and cardiovascular and metabolic health. Do not start, stop, change, or add any medication - including an aromatase inhibitor, a dopamine agonist, or a change to your testosterone dose - without the clinician who manages your treatment, and seek care for persistent sexual dysfunction rather than self-adjusting. Related hormone markers are covered at the bloodwork hub.
This contributor writes under a pseudonym. The photograph above is a stylized portrait, not a real image of the writer. See our About page for details on our editorial team and anonymity policy.


