Testosterone Enanthate

TESTOSTERONE ENANTHATE: THE MOST STUDIED STEROID, IN NUMBERS
Testosterone enanthate is plain testosterone with a 7 carbon ester that slows its release. It is also the ester behind the best dose trials in steroid science, from 25 to 600 mg a week.
This guide covers the half life and enanthate vs cypionate. It shows what each dose did to muscle, blood, lipids, mood and fertility, and how cycles look in practice. Study figures come from PubMed. Practice figures are marked as practice. The wider family is in testosterone steroids.
Testosterone enanthate in three numbers
Three figures from the trials frame everything below: how long it lasts, what it builds, and what it costs.
Enanthate ester, as cited in a 2022 review (PMID 36644692).
Fat free mass in young men, no training (PMID 11701431).
Lower doses left HDL unchanged (PMID 11788637).
Study figures come from PubMed papers. What athletes do in practice is not studied; where we describe it, we say so.
What this testosterone enanthate guide covers
Pharmacology: the ester, testosterone enanthate half life and enanthate vs cypionate.
Dose response trials from 25 to 600 mg a week: muscle, strength, blood, lipids, mood.
Fertility, recovery and the cycles athletes report, next to studied doses.
Not coveredA protocol. Nothing here is a dose to take. Practice figures describe what people do, with personal and unstudied risk.
Buying or testing products. Products sold for sport are unregulated.
What testosterone enanthate is
The hormone inside is the same testosterone your body makes. The ester is a 7 carbon chain attached to it, which holds the drug in the oil depot and releases it slowly (PMID 36644692).
Once released, the ester is cut off. From then on the body handles it like its own testosterone: some becomes DHT, some becomes estradiol (PMID 36644692).
Doctors use it for low testosterone. Typical medical doses were 200 mg every 2 weeks into muscle (PMID 10522982). Another option is 50 to 100 mg a week under the skin with an auto injector (PMID 30296416).
Researchers use it because it is easy to dose precisely. That is why most controlled steroid data on healthy men comes from this one ester (PMID 11701431, 8637535).
| Property | Testosterone enanthate |
|---|---|
| Ester | 7 carbon chain (PMID 36644692) |
| Half life | About 4.2 days (PMID 36644692) |
| Medical doses | 200 mg every 2 weeks IM; 50 to 100 mg a week SC (PMID 10522982, 30296416) |
| Doses in trials | 25 to 600 mg a week (PMID 11701431) |
| Converts to | DHT and estradiol (PMID 36644692) |
Testosterone enanthate half life and the peaks between shots
Unmodified testosterone lasts about 10 minutes after injection. The propionate ester stretches that to about 1 day, enanthate to about 4.2 days (PMID 36644692).
A half life of 4 days still gives a peak and a dip. In hypogonadal men on 200 mg every 2 weeks, testosterone and estradiol ran above normal for several days after each shot (PMID 10522982).
Morning hormone levels were normal in only 19 to 84 percent of those men. On a daily patch it was 77 to 100 percent (PMID 10522982).
Smaller, more frequent doses flatten the curve. With 50 to 100 mg a week under the skin, 92.7 percent of men averaged 300 to 1,100 ng/dL. None topped 1,800 ng/dL at week 12 (PMID 30296416).
Dose sets the level. With their own production switched off, 25 mg a week gave a trough of 253 ng/dL; 600 mg gave 2,370 ng/dL (PMID 11701431).
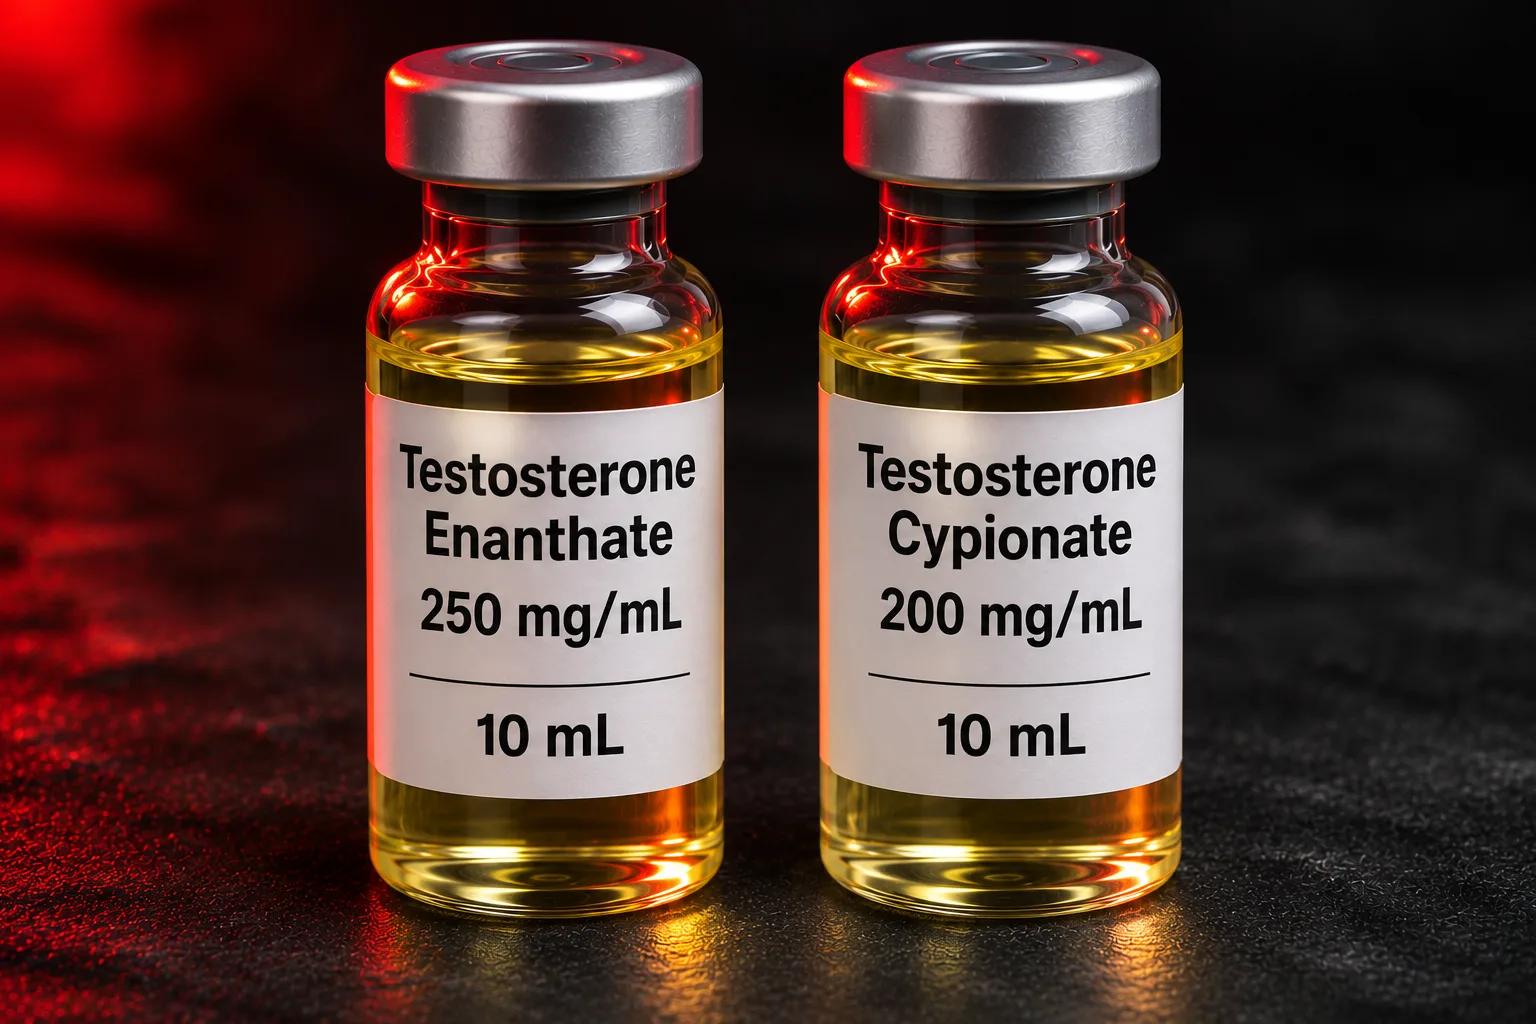
Testosterone enanthate vs cypionate
This is one of the most searched questions about the ester. The short answer: research treats them as the same drug.
Cypionate carries an 8 carbon ester, enanthate a 7 carbon one. Both deliver the same testosterone, both are oil based injections.
A 2022 meta analysis of 29 randomized trials pooled the two together as one group. That group raised hematocrit 4.0 percent over placebo (PMID 34445892).
The classic trials also cross over. The muscle trials used enanthate (PMID 8637535); a key mood trial used cypionate at the same 600 mg a week (PMID 10665615).
| Point | Enanthate | Cypionate |
|---|---|---|
| Ester length | 7 carbons (PMID 36644692) | 8 carbons |
| Hematocrit in trials | Pooled: +4.0% vs placebo (PMID 34445892) | Same pooled group (PMID 34445892) |
| Key trial | Muscle and strength, 600 mg (PMID 8637535) | Mood, 600 mg (PMID 10665615) |
| Athletes report | Used interchangeably (practice) | Used interchangeably (practice) |
What testosterone enanthate does to muscle and strength
The landmark trial. 43 men got 600 mg a week or placebo for 10 weeks, with or without lifting. Testosterone plus training added 6.1 kg of fat free mass (PMID 8637535).
Even without training, testosterone beat placebo. Bench press rose 9 kg against minus 1 kg, and squat 16 kg against 3 kg (PMID 8637535).
With training, the gains were bigger: bench press up 22 kg and squat up 38 kg (PMID 8637535).
Dose response. 61 young men were followed for 20 weeks. Fat free mass rose 3.4 kg at 125 mg, 5.2 kg at 300 mg and 7.9 kg at 600 mg a week (PMID 11701431).
Leg press strength and leg power rose with dose too. Muscle fatigue and strength per unit of muscle did not change (PMID 12679426).
Older men respond the same. Men aged 60 to 75 gained 4.2, 5.6 and 7.3 kg at 125, 300 and 600 mg a week. The authors saw 125 mg as the best trade off (PMID 15562020).
Testosterone enanthate side effects: blood, lipids and estradiol
Most testosterone enanthate side effects follow the dose. These are the ones measured in trials.
Thicker blood
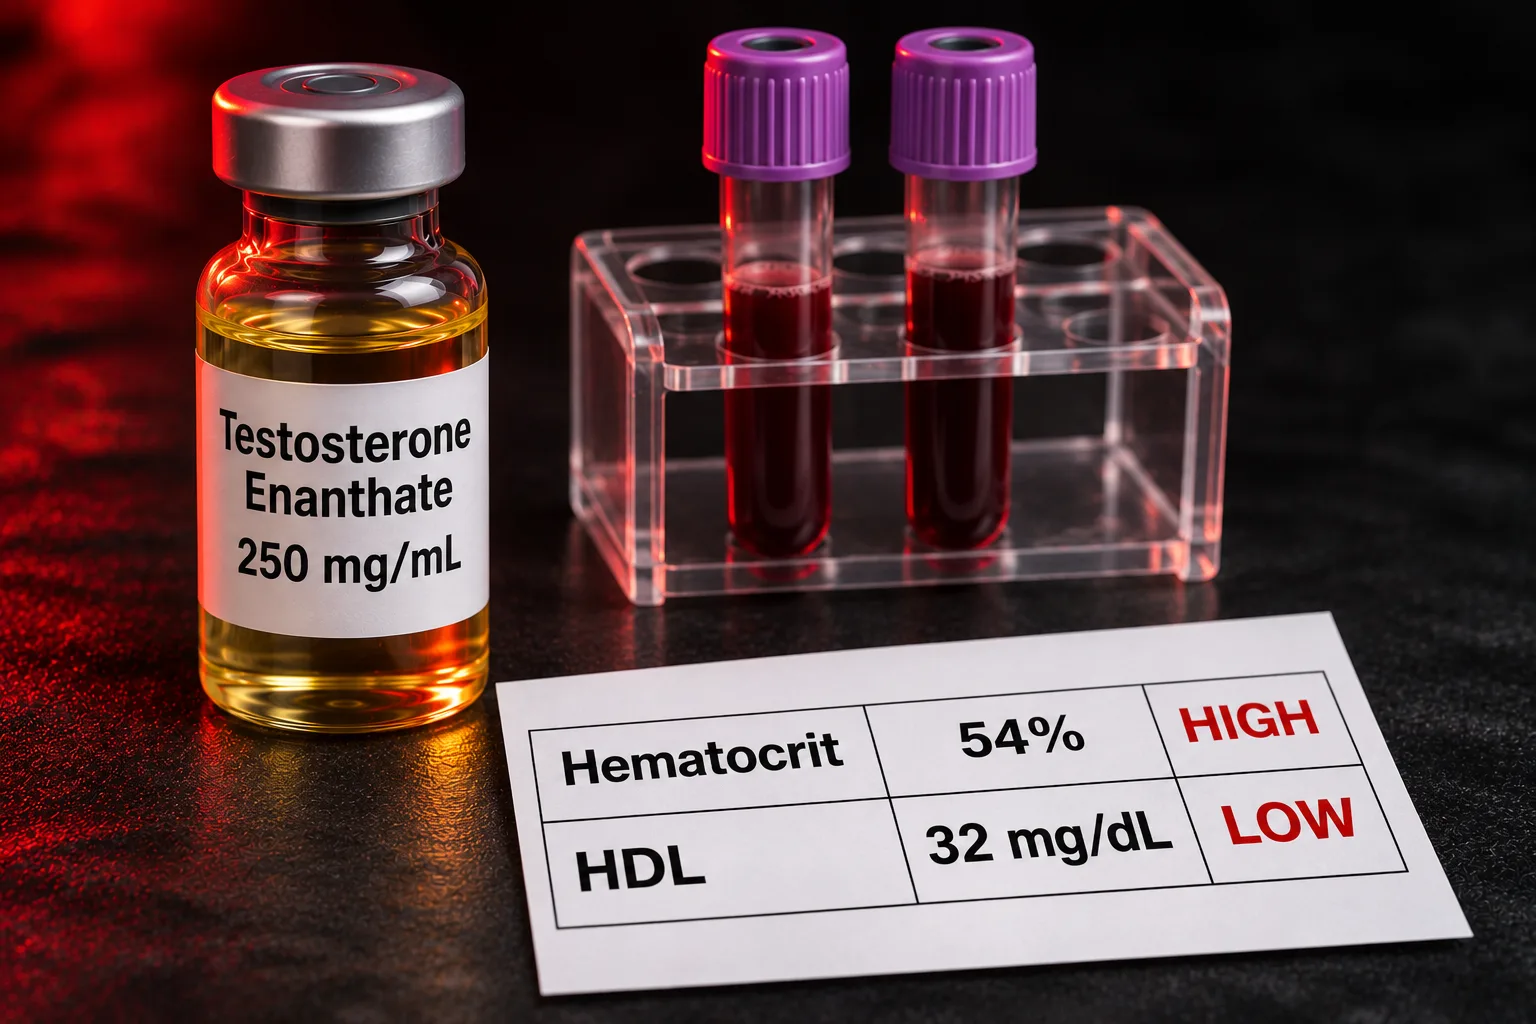
Hemoglobin and hematocrit rose with dose in young and older men, more in the older (PMID 18160461). At 600 mg, hemoglobin rose 1.4 g/dL in young men (PMID 36644692).
Abnormal hematocrit on shots
43.8% of men on 200 mg every 2 weeks vs 15.4% on a patch (PMID 10522982).
HDL falls at high dose
Down 8 mg/dL only at 600 mg a week; LDL, triglycerides and insulin sensitivity did not change (PMID 11788637).
Estradiol peaks
Above normal for days after each shot (PMID 10522982).
Older men pay more. At 600 mg a week, hemoglobin rose 29.4 g/L in men aged 60 to 75. Hematocrit above 54 percent, leg swelling and prostate events were more frequent than in young men (PMID 15562020).
Prostate and skin. In healthy men up to 600 mg a week, PSA and prostate volume did not change over 20 weeks (PMID 36644692).
Estradiol is not the enemy. It is needed for libido, erections and sperm production in men (PMID 26908066). Crushing it to zero has its own costs.
Testosterone enanthate and mood: roid rage tested
Two controlled trials tested the "roid rage" idea at 600 mg a week.
In 43 men on testosterone enanthate for 10 weeks, anger scores did not change, by self report or by partner report (PMID 8855834).
In 56 men on cypionate, same hormone and same top dose, mania scores rose on average. 84 percent had minimal effects, 12 percent became mildly hypomanic and 4 percent markedly so (PMID 10665615).
The 8 men who reacted did not differ at baseline from those who did not. Nobody could predict who would react (PMID 10665615).
Fertility and recovery after testosterone enanthate
Testosterone enanthate is a tested male contraceptive. In a WHO trial, 271 men took 200 mg a week (PMID 1977002).
157 men stopped producing sperm, on average after 120 days. After stopping, sperm took a median 3.7 months to reach 20 million per mL, and 6.7 months to return to baseline (PMID 1977002).
Not every man went to zero. At 200 mg a week, about two out of three men became azoospermic (PMID 36644692).
Real cycles last longer and stack more drugs. In 641 men seen after stopping steroids, only 48.2 percent had fully normal hormones (PMID 38102386).
Those who used post cycle therapy recovered faster: a median 13 weeks against 26 weeks. The authors still call it unproven and not recommended (PMID 38102386).
Testosterone enanthate cycle and stacks: studied vs practice
This section describes practice, not advice. Doses athletes report are not studied in healthy people beyond 600 mg a week. Using them is a personal, unstudied risk, and every body responds differently.
Trials covered 25 to 600 mg a week for up to 20 weeks (PMID 11701431). In a Dutch steroid clinic, cycles had a median of three drugs for a median 10 weeks, and testosterone was the most common (PMID 29845939).
Users commonly describe a first cycle of 250 to 500 mg a week for 10 to 16 weeks, often split into two shots a week. That is practice, not a studied protocol.
| Item | In studies | Athletes report (practice, unstudied) |
|---|---|---|
| Weekly dose | 25 to 600 mg (PMID 11701431) | Commonly 250 to 500 mg |
| Length | 10 to 20 weeks (PMID 8637535, 11701431) | Commonly 10 to 16 weeks |
| Injections | Weekly in trials (PMID 11701431) | Often split twice a week |
| After the cycle | Sperm back in 3.7 to 6.7 months (PMID 1977002) | Recovery protocols, unproven (PMID 38102386) |
| Stack | Why athletes use it | What the evidence says |
|---|---|---|
| Test E + Deca | Classic bulk; testosterone covers libido | Common pairing in clinic users (PMID 29845939) |
| Test E + Dianabol | Fast start to a bulk | No trial of this pair; see the Dianabol guide |
| Test E + trenbolone | Hard mass or recomp | Common in clinic users; no trial (PMID 29845939) |
| Test E + Anavar | Cutting phase | No trial of this pair; see the Anavar guide |
| Test E + Winstrol | Cutting, show prep | No trial of this pair; see the Winstrol guide |
Bloodwork that catches testosterone enanthate side effects
Each measured effect has a lab marker. This is what moved in the trials above.
| Marker | What moved | Guide |
|---|---|---|
| Hematocrit, hemoglobin | Up with dose; +1.4 g/dL at 600 mg (PMID 18160461, 36644692) | CBC markers |
| HDL | −8 mg/dL at 600 mg only (PMID 11788637) | Lipid panel |
| Estradiol | Above normal for days after shots (PMID 10522982) | Estradiol |
| LH, FSH, testosterone | Suppressed; normal in 48.2% after stopping (PMID 38102386) | Suppression |
| PSA | No change up to 600 mg, 20 weeks (PMID 36644692) | 7 markers |
7 proven facts about testosterone enanthate
1. Half life about 4.2 days. Versus 10 minutes for plain testosterone (PMID 36644692).
2. Muscle follows dose. +3.4, 5.2, 7.9 kg at 125, 300, 600 mg a week (PMID 11701431).
3. Training doubles up. +6.1 kg fat free mass in 10 weeks with lifting (PMID 8637535).
4. HDL held until 600 mg. Then fell 8 mg/dL (PMID 11788637).
5. Hematocrit rises with dose. More in older men (PMID 18160461).
6. Most men stay calm, a few do not. 4% markedly hypomanic at 600 mg (PMID 10665615).
7. Fertility returns slowly. Median 3.7 months to 20 million per mL (PMID 1977002).
Testosterone enanthate: frequently asked questions
What is the testosterone enanthate half life?
About 4.2 days after injection, against about 10 minutes for unmodified testosterone and about 1 day for propionate (PMID 36644692).
Testosterone enanthate vs cypionate: which is better?
Neither in practice. Both deliver the same hormone; a meta analysis of 29 trials pooled them as one group, raising hematocrit 4.0% over placebo (PMID 34445892).
How much muscle does testosterone enanthate add?
In 20 weeks, 3.4 kg at 125 mg, 5.2 kg at 300 mg and 7.9 kg at 600 mg a week (PMID 11701431). With lifting, 600 mg added 6.1 kg in 10 weeks (PMID 8637535).
What are the main testosterone enanthate side effects?
Rising hematocrit, estradiol peaks and lower HDL at 600 mg. Also suppressed sperm production and, in a few men, mood changes (PMID 18160461, 10522982, 11788637, 10665615).
Does testosterone enanthate cause roid rage?
Not in most men. At 600 mg a week anger did not change in one trial (PMID 8855834); in another, 4% became markedly hypomanic (PMID 10665615).
Does testosterone enanthate affect fertility?
Yes. 200 mg a week stopped sperm production in most men; recovery to 20 million per mL took a median 3.7 months (PMID 1977002).
How often is testosterone enanthate injected?
Medically every 2 weeks IM or weekly under the skin (PMID 10522982, 30296416). Many athletes split doses twice a week; that is practice, not studied.
What dose do athletes use in a cycle?
Trials went up to 600 mg a week. Users commonly report 250 to 500 mg for 10 to 16 weeks. That is practice, not a recommendation, and a personal risk.
Sources and further reading
Every study figure on this page comes from one of the 16 papers below, checked against PubMed on 1 November 2026. Practice figures are marked as practice. Reference links are dofollow to support open science.
More from the steroids series
Four guides that sit closest to this one.
Final Educational Note
This article is educational and is not medical advice. It reports what trials, clinics and reviews say about testosterone enanthate. Practice doses are described, not recommended, and carry personal, unstudied risk.
Headaches with a red face, chest pain, one sided leg swelling or sudden mood swings on a cycle need a doctor. More guides sit on the steroids hub. Read more on the about page and in the full disclaimer.


