High Estrogen Symptoms on Steroids: 7 Key Signs
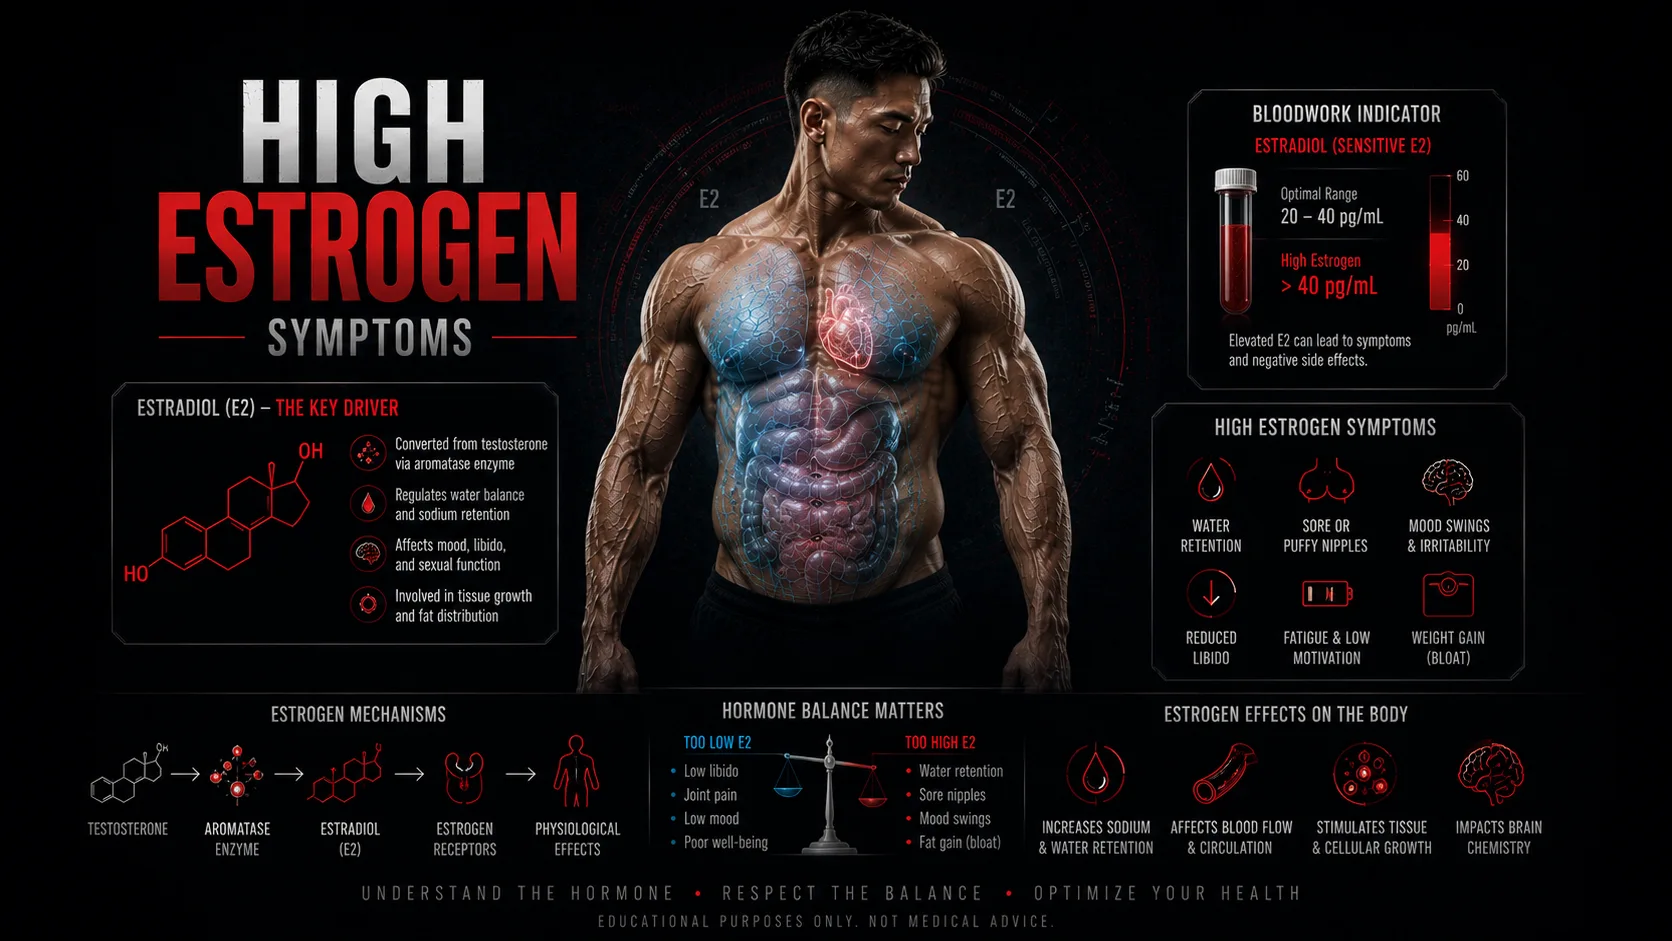
HIGH ESTROGEN SYMPTOMS ON STEROIDS: 7 KEY SIGNS
High estrogen on an aromatising cycle shows up as fluid retention, puffy or tender nipples, mood swings, disturbed sleep and a libido that drops while testosterone is high. In the HAARLEM study of 100 men followed through a real cycle, 56 percent reported fluid retention, 36 percent agitation and 19 percent developed gynecomastia, and in a controlled dose study estradiol rose in step with every increase in testosterone. This guide ranks the signs by how specific they are, explains why estradiol climbs, and shows why the mirror cannot separate high estrogen from crashed estrogen, which feels almost the same.
Data in brief
Three numbers frame high estrogen on cycle, the state behind most high estrogen symptoms: how often the signs actually show up in men running real cycles, how tightly estradiol tracks the testosterone dose, and how often the sign everyone fears becomes tissue.
In the HAARLEM study, 100 men were followed before, during and after a self-chosen cycle. Fluid retention was the most common negative effect during the cycle at 56 percent, followed by agitation at 36 percent (PMID 33038020).
In 103 men given five weekly doses of testosterone enanthate from 25 to 600 mg with their own production switched off, total and free estradiol rose dose dependently, and conversion was 40 percent more efficient in older men (PMID 20534765).
Gynecomastia was observed in 19 percent of the HAARLEM cohort and acne in 28 percent. Neither the dose nor the cycle length predicted who got which side effect (PMID 33038020).
Every figure comes from the abstracts of the twelve papers listed at the end. Nothing here is a protocol for high estrogen: the only management step this page endorses is a sensitive estradiol test read by a clinician.
What this guide covers
The signs of high estrogen on a steroid cycle, ranked by how specific each one is, because half of them also appear when estrogen is too low.
Why high estradiol happens: aromatisation, dose, body fat and age, with the controlled data behind each.
High estrogen against low estrogen, side by side, and why a blood test is the only way to tell them apart.
What aromatase inhibitors do to the numbers in controlled trials, and why overshoot is the more common outcome.
Not coveredCrashed estrogen in detail. The opposite problem has its own page, low estrogen on cycle.
Treating formed gynecomastia. Tissue that already exists is covered in how to get rid of gyno.
Estradiol on prescription testosterone. The therapeutic-dose picture lives on estradiol on TRT. No doses, protocols or targets appear here.
What are the signs of high estrogen on a steroid cycle?
The signs of high estrogen on a steroid cycle are watery fluid retention, puffy or tender nipples, a bloated midsection, faster fat gain, mood swings and irritability, disturbed sleep, and a libido that drops even though testosterone is high. They appear because aromatising compounds convert part of the dose into estradiol, and estradiol rises in proportion to the dose (PMID 20534765). Two of them, fluid and nipple tissue, point at high estradiol directly; the rest overlap with other causes and need a blood test to interpret.

The chart is what makes this page different from a symptom list: it is measured. Smit and colleagues followed 100 men who were about to start a cycle of their own choosing, with clinic visits before, at the end, three months after and one year after. Every one of them reported at least one negative effect. Fluid retention led at 56 percent and agitation at 36 percent during the cycle; decreased libido peaked after it at 58 percent; gynecomastia was observed in 19 percent (PMID 33038020).
Two details from that cohort matter for anyone reading their own body. First, the dose and the cycle length were not associated with the type or severity of side effects, so a "moderate" cycle is not protection. Second, the effects had returned to baseline a year after the start, which is the honest reassurance: high estrogen on cycle is usually a reversible state, and high estrogen symptoms fade with it, provided it is not treated with guesswork.
The seven signs, ranked by how much they mean
Not every sign carries the same weight. The table sorts them by specificity: whether the sign points at high estradiol, at low estradiol, or at almost anything.
| Sign | What it feels like | Why it happens | Specificity |
|---|---|---|---|
| 1. Puffy, itchy or tender nipples | Sensitivity or a soft swelling behind the nipple, often one side first | Estrogens stimulate breast tissue while androgens inhibit it; the balance decides (PMID 25112235) | High estradiol |
| 2. Watery fluid retention | Smooth, puffy look, tight rings, weight up within days of a dose change | Most common effect on cycle, 56 percent in HAARLEM (PMID 33038020) | High estradiol, with a sodium component |
| 3. Faster fat gain | Softness despite training and diet holding steady | In controlled work, estrogen status governed fat mass more than testosterone status did (PMID 24024838) | Direction depends on the number |
| 4. Mood swings, irritability | Short fuse, emotional volatility | Agitation reported by 36 percent during the cycle (PMID 33038020); also reported when estradiol is crashed | High and low |
| 5. Libido drops while testosterone is high | Desire falls, erections weaker, in the middle of a cycle | Estradiol contributes to sexual function in men at both extremes (PMID 24024838) | High and low |
| 6. Disturbed sleep | Waking, restlessness, night sweats | Reported with high and with crashed estradiol; also with stimulants and blood pressure | Non specific |
| 7. Bloated midsection and rising blood pressure | Waist up, readings up on a home cuff | Fluid retention raises blood volume; androgens raise pressure on their own as well | Non specific |
Read the table from the top. Nipple changes and watery retention are the two high estrogen signs worth acting on, and acting means testing. Everything from row three down is real, but each of those signs also appears when estradiol has been driven too low with an inhibitor, which is why the same list of symptoms sends one man to add an aromatase inhibitor and another to stop one.
Why high estradiol happens on cycle
Aromatase converts a share of testosterone to estradiol. Lakshman (2010) switched off endogenous production in 51 young and 52 older men and gave five weekly doses of testosterone enanthate, 25 to 600 mg, for five months. Total and free estradiol rose dose dependently in both age groups. The conversion followed saturable kinetics, and the maximum rate was 40 percent higher in older men (PMID 20534765). More testosterone in means more estradiol out, and high estrogen is the predictable result; the enzyme does not need permission.
Body fat is the second lever. In 64 severely obese men, BMI correlated positively with estradiol and negatively with testosterone. Two years after gastric bypass, BMI fell by 16.6 points, estradiol fell by 8.1 pg/mL and total testosterone rose by 311 ng/dL, while the non-surgical group barely moved (PMID 19174499). Fat tissue is where a lot of aromatisation happens, so the same dose produces more high estrogen in men who carry more of it.
A different dataset from the chart above: what changed over two years in obese men after gastric bypass against a non-surgical comparison group. Bars show the change relative to the largest value in each pair. Hammoud 2009, PMID 19174499.
Total testosterone rose 310.8 ng/dL after surgery against 14.2 ng/dL without it, and sexual quality of life improved. The mechanism is the one that matters on cycle: less fat, less aromatase, less estradiol from the same testosterone.
Age is the third lever, and the least discussed. The same Lakshman dose study found the aromatase maximum rate 40 percent higher in men aged 59 to 75 than in men aged 19 to 35, which is why a man in his forties running a dose he tolerated at 25 can meet high estrogen for the first time (PMID 20534765). Compound choice sits on top of all three: non-aromatising compounds add androgen without adding estradiol, aromatising ones add both, which is why high estrogen tracks the stack as much as the dose.
High estrogen or low estrogen? The comparison that decides it
This is the section that saves cycles. Most of the mental and sexual high estrogen signs are shared by both directions, and the physical signs are the only ones that separate them. The table puts them side by side.
| Feature | High estradiol | Low or crashed estradiol | Use it? |
|---|---|---|---|
| Water | Puffy, smooth, watery, weight up | Flat, dry, deflated | Yes |
| Nipples | Tender, itchy, puffy | Unaffected | Yes |
| Joints | Comfortable, sometimes better than off cycle | Aching, cracking, dry | Yes |
| Skin | Oilier, acne in 28 percent of a cycle cohort | Dry | Leans, not proof |
| Libido and erections | Down | Down | No |
| Mood | Volatile, irritable | Flat, anxious, low | No |
| Sleep | Disturbed | Disturbed | No |
| Timing | Follows a dose increase of an aromatising compound | Follows adding or raising an aromatase inhibitor | Yes |
| Sensitive estradiol assay | High for the testosterone level | Low | Decides it |
The shared rows are the dangerous ones. A man whose libido and mood fall in week six has no way of knowing, from those two high estrogen signs alone, whether estradiol is high or crashed, and the two fixes are opposites. The full picture of the other direction is on the crashed estrogen page; the answer to which one you have is in the last row, and only there.
From tender nipples to gyno: how the sign becomes tissue
Gynecomastia is the high estrogen sign lifters fear most, and the physiology is simple. Estrogens stimulate the growth of male breast tissue while androgens inhibit it, so most cases come from deficient androgen action or excessive estrogen action at the breast (PMID 25112235). On an aromatising cycle the androgen side is high, which means estradiol has to climb very high, or the tissue has to be unusually sensitive, before growth begins. That is why the early signal is tenderness and itch rather than a lump.
Braunstein's review in the New England Journal of Medicine and the Narula and Carlson review both make the same point about timing: early, tender tissue is still reversible, established fibrous tissue is not, and the difference is months, not years (PMID 17881754, PMID 25112235). The practical reading is that nipple sensitivity on cycle is the one high estrogen symptom that should shorten the interval to a blood test rather than lengthen the wait to see.
What this page does not do is tell anyone how to treat it. A firm lump that persists after the cycle is a different problem with its own page, how to get rid of gyno, and a clinical examination is the only way to distinguish glandular tissue from fat, or from the rare but real male breast cancer that the same reviews caution about (PMID 25112235).
What an aromatase inhibitor actually does to the numbers
Aromatase inhibitors are the standard answer to high estrogen: they lower estradiol and raise testosterone in men, which is exactly why they are so easy to overshoot with. The controlled data come from older men at prescription doses, and they show both the size of the effect and its cost.
The drop is fast and large
Twelve weeks of anastrozole in 37 men aged 62 to 74 moved estradiol from 26 to 17 pg/mL and total testosterone from 343 to 572 ng/dL (PMID 15001605). That is a prescription dose in men who started with normal estradiol; on cycle the starting point is higher and the response is not smaller.
Bone pays for a low number
One year of anastrozole took estradiol from 15 to 12 pg/mL and lumbar spine bone density fell from 1.121 to 1.102 g/cm2 while the placebo group gained, P 0.0014 (PMID 19820017). The authors concluded that aromatase inhibition does not improve the skeleton in ageing men; it costs it.
Sexual function did not improve with lower estradiol
In the 12 week trial, sexual function scores did not change when estradiol fell and testosterone rose (PMID 15001605). Lower estrogen is not a libido treatment, and in the Finkelstein data estradiol contributed to sexual desire in its own right (PMID 24024838).
Fat is an estrogen effect, not only a testosterone effect
When 198 men had their own production suppressed and were given graded testosterone with or without anastrozole, fat rose in the groups that lost estrogen action, independent of androgen status (PMID 24024838). Chasing a low estradiol number to "stay dry" works against that finding.
The overlap makes overshoot invisible
The signs of crashed estradiol, low libido, flat mood, poor sleep, are the same signs that prompted the inhibitor. A man who overshoots typically reads the result as "still high" and adds more. The comparison table above exists for this reason.
These are prescription drugs with a defined use
The review of aromatase inhibitors in men lists their established uses and warns that long term data on safety and efficacy in men are limited (PMID 21693046). Their place in a cycle is a decision for a clinician holding a sensitive estradiol result, not a forum protocol.
None of this argues that high estradiol should be ignored. It argues that the tool most people reach for is precise enough to cause the opposite problem in weeks, and that the only thing separating the two is a number nobody has looked at.
Measure it: the test that separates high estrogen from a guess
The standard estradiol immunoassay was built for female concentrations and reads poorly in the male range. In 313 men aged 22 to 91, immunoassay agreed with mass spectrometry at R 0.90 for testosterone but only R 0.63 for total estradiol (PMID 18338096). The Endocrine Society position statement says plainly that routine methods are not adequate for the low concentrations found in men (PMID 23463657).
1. Ask for the sensitive assay. LC-MS/MS, or an assay validated for male concentrations. A standard panel result in the male range is the reason two labs disagree by half.
2. Read estradiol next to testosterone. Estradiol rises with the dose (PMID 20534765), so a high estradiol number in isolation may be proportionate to the testosterone beside it. The ratio, not the estradiol alone, is what a clinician interprets.
3. Time it to the change. Signs that follow a dose increase of an aromatising compound argue for high estrogen; signs that follow adding an inhibitor argue for the opposite. Draw blood when the signs are present, not weeks later.
4. Put it in a baseline and a schedule. The number only means something against your own pre-cycle value, which is why estradiol belongs in the baseline panel and in the same draw as the rest of the hormone markers, read by someone qualified to act on it.
5. Change one thing. Whatever a clinician decides, one change followed by a repeat test is interpretable. Two changes at once, or a change made on feel, is how the HAARLEM effects that "returned to baseline" turn into problems that do not.
Verdict: which high estrogen symptoms to act on
High estrogen on an aromatising cycle is common, measured and usually reversible, and so are high estrogen symptoms: 56 percent of a real cohort held fluid, 19 percent developed gynecomastia, and a year later prevalence was back to baseline (PMID 33038020). Two signs deserve action, tender or puffy nipples and watery retention, and the action is a sensitive estradiol test read next to testosterone.
The signs of high estrogen on a steroid cycle that people treat most aggressively, low libido and low mood, are the least specific and are shared with the opposite state. The trials on aromatase inhibitors show a fast, large drop in estradiol, a cost to bone and no gain in sexual function (PMID 15001605, PMID 19820017), so the harm from guessing wrong runs in both directions.
If the rested, sensitive estradiol result shows high estradiol for the testosterone beside it, that is a conversation with a clinician about the compound and the dose. If it is not, the high estrogen symptoms you suspected have another cause and the fix is not less estrogen. The wider set of effects that travel with these ones is on the PED side effects hub.
Frequently asked questions
What are the signs of high estrogen on a steroid cycle?
Fluid retention, puffy or tender nipples, a bloated midsection, faster fat gain, mood swings, disturbed sleep and a libido that drops while testosterone is high. In 100 men followed through a real cycle, fluid retention was reported by 56 percent and agitation by 36 percent during the cycle, and gynecomastia was observed in 19 percent (PMID 33038020). Nipple changes and watery retention are the two signs that point at estradiol specifically.
How do I know if my estrogen is high or low on cycle?
Not from libido, mood or sleep, because those fall in both directions. Watery puffiness and tender nipples argue for high estradiol; a flat, dry look with aching joints argues for crashed estradiol; and timing helps, since high follows a dose increase and low follows adding an inhibitor. The only reliable answer is a sensitive estradiol test read next to testosterone (PMID 23463657).
Why does estradiol rise when I take testosterone?
Because aromatase converts part of it. In 103 men given five weekly doses of testosterone enanthate from 25 to 600 mg, total and free estradiol rose dose dependently, and the conversion rate was 40 percent higher in older men (PMID 20534765). Body fat adds to it: in obese men, BMI correlated positively with estradiol and weight loss after surgery cut estradiol by 8.1 pg/mL (PMID 19174499).
Does high estrogen on cycle always lead to gyno?
No. Gynecomastia was observed in 19 percent of a 100 man cycle cohort, not all of it (PMID 33038020). Estrogens stimulate breast tissue and androgens inhibit it, so growth depends on the balance and on individual sensitivity (PMID 25112235). Early tenderness is the reversible stage; established tissue is not, which is why the sensitive sign is worth a test.
Can I take an aromatase inhibitor if I have high estrogen symptoms?
That is a clinician's decision on a sensitive estradiol result, and the trials explain why. Twelve weeks of anastrozole took estradiol from 26 to 17 pg/mL and did not improve sexual function (PMID 15001605), and one year took spine bone density down while placebo gained (PMID 19820017). Most of the symptoms that prompt the drug also appear when estradiol is crashed, so guessing overshoots.
Which estradiol test should I ask for?
A sensitive assay, ideally LC-MS/MS or one validated for male concentrations. In 313 men, the standard immunoassay agreed with mass spectrometry at only R 0.63 for estradiol against 0.90 for testosterone (PMID 18338096), and the Endocrine Society states that routine methods are not adequate for the concentrations found in men (PMID 23463657).
Does high estrogen make you hold water and gain fat?
Fluid retention was the most common negative effect during a cycle at 56 percent (PMID 33038020). Fat is more subtle: in 198 men with their own production suppressed, body fat rose in the groups that lost estrogen action rather than the groups with more of it (PMID 24024838), so estradiol both high and crashed can move body composition, in different ways.
How long do high estrogen symptoms last after the cycle?
In the HAARLEM cohort, the prevalence of observed effects had returned to baseline one year after the start of the cycle, and decreased libido peaked after the cycle at 58 percent rather than during it (PMID 33038020). Fluid moves within days of a dose change; tissue that has formed does not, which is the reason nipple changes are treated as an early warning.
Sources and further reading
Every figure on this page comes from one of the twelve papers below, each checked against its PubMed record on 25 September 2026. Reference links are dofollow to support open science.
Keep reading
Four pages that carry this further: the opposite problem, the tissue endpoint, the baseline number and the therapeutic-dose version of the same question.
Final Educational Note
This article is educational and is not medical advice. It reports what a prospective cycle cohort and controlled trials measured about estradiol in men, including how often high estrogen signs occur and what aromatase inhibitors do to the numbers. It does not recommend any compound, dose, inhibitor or target, and it is not an encouragement to use anabolic steroids, which carry serious health and legal risks. More guides sit on the PED side effects hub.
Tender breast tissue, a lump, or symptoms that do not fit the pattern described here are clinical questions for a physician. Read more about how this site works on the about page and in the full disclaimer.


