How to Get Rid of Gyno: 5 Proven Steps That Work
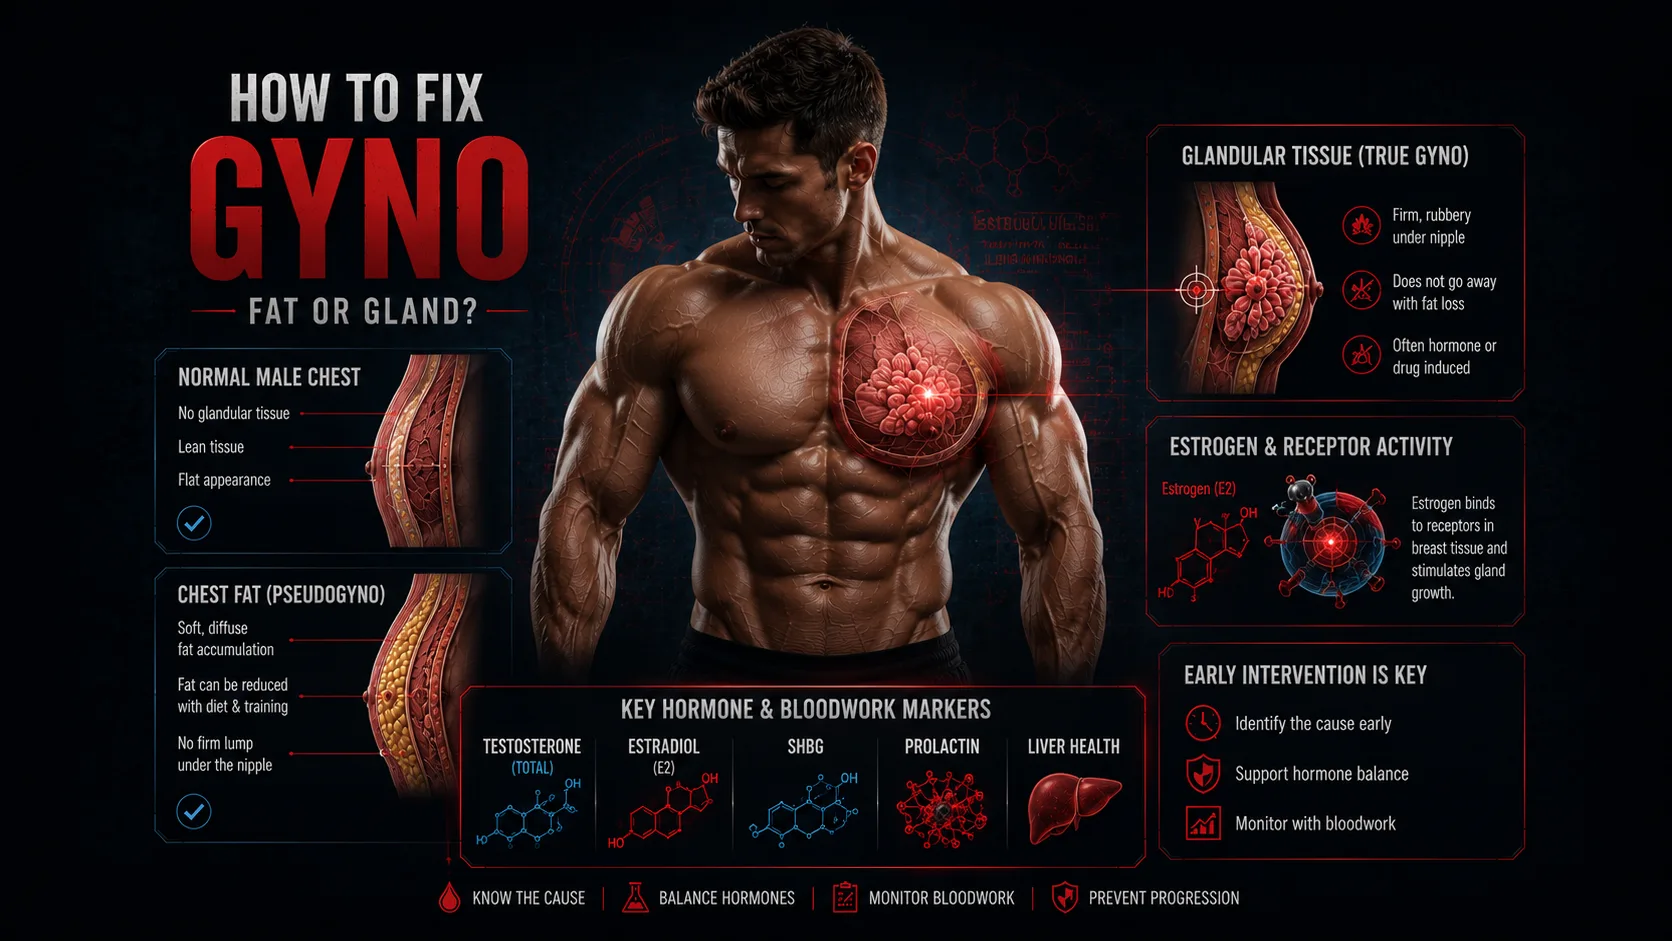
HOW TO GET RID OF GYNO: 5 PROVEN STEPS THAT WORK
How to get rid of gyno comes down to one question: how old is the tissue? Can you get rid of gyno without surgery? Yes, when it is caught early. In 68 men with idiopathic gynecomastia, tamoxifen produced complete resolution in 78 percent (PMID 10651345); in 38 adolescents, an estrogen receptor modulator improved 86 to 91 percent of cases (PMID 15238910). Gynecomastia hit 19 percent of the 100 men followed through a steroid cycle (PMID 33038020), and once the tissue turns fibrous the only measured fix is excision. This guide sets out what the trials found for each option, without a protocol, because the trigger is nearly always the high estrogen state that a cycle creates.
Data in brief
Three numbers frame how to get rid of gyno: how often a cycle causes it, how well the medical option works when tissue is new, and what surgery costs in complications when it is not.
In 100 men followed prospectively through an anabolic steroid cycle, gynecomastia was observed in 19 percent, alongside acne in 28 percent, and dose and cycle length did not predict who got it (PMID 33038020). In a Dutch clinic of 180 users, 34 percent reported gynecomastia (PMID 29845939).
In 68 men with idiopathic gynecomastia, median size 3 cm and median duration 3 months, tamoxifen produced complete resolution in 18 of 23 (78.2 percent) against 8 of 20 (40 percent) on danazol (PMID 10651345). Early tissue is the tissue that answers.
Across 94 studies and 7,294 patients, complications were recorded in 30.64 percent of surgical excision cases, 14.87 percent of aspiration cases and 11.76 percent when the two were combined (PMID 35138423). Surgery works, and it is not free.
Every figure is taken from the abstracts of the thirteen papers at the end. Drug names appear only where a trial used them; no dose, schedule or protocol is given here.
What this guide covers
Whether you can get rid of gyno without surgery, and what decides how to get rid of gyno at all: the age of the tissue.
What the trials measured on how to get rid of gyno for tamoxifen, raloxifene, danazol and anastrozole, and what each number means for a lifter rather than a prostate patient or an adolescent.
When surgery is the only way to get rid of gyno, and what the complication data say about the technique.
The five mistakes that turn a reversible case of how to get rid of gyno into a surgical one.
Not coveredWho gets gyno on cycle and the early warning signs. That is gynecomastia risk on steroids; this page starts once tissue is there.
The hormone state behind it. The signs and numbers are on high estrogen symptoms on steroids.
Any protocol. No SERM, aromatase inhibitor or dose instructions. Trial results are reported; treatment is a prescriber's decision.
Can you get rid of gyno without surgery?
Yes, if the tissue is recent, and the odds of being able to work out how to get rid of gyno without surgery fall with every month it sits there. The clearest human data on how to get rid of gyno are not from steroid users, because nobody has run a trial in them, but they measure the same tissue. In 68 men with idiopathic gynecomastia, median duration three months, the answer to can you get rid of gyno was measured directly: tamoxifen gave complete resolution in 78.2 percent and danazol in 40 percent (PMID 10651345).
In 38 adolescents whose gynecomastia had lasted a mean of 28.3 months, tamoxifen improved 86 percent and raloxifene 91 percent, with a reduction of more than half in 41 and 86 percent respectively (PMID 15238910).
The condition on that answer is the reason a page on how to get rid of gyno exists at all. The clinical reviews describe an early proliferative phase, when the gland is growing and responds to blocking the estrogen receptor, and a later fibrotic phase, when the gland has been replaced by fibrous tissue that no drug shrinks (PMID 17881754).
The adolescent series is a useful correction to the forum rule that twelve months is the cut-off: at a mean of 28 months, most still improved (PMID 15238910). The honest reading on how to get rid of gyno is that the window is longer than people think and shorter than they hope, and nobody can tell you where you are in it without an examination.
So how to get rid of gyno without surgery is a question with a time stamp, and can you get rid of gyno at all is answered by the same clock. Ask how to get rid of gyno in the first weeks and the trial data are on your side. Ask it after a year of waiting and a decision about excision is what a clinician will be weighing.

Is it gyno, or is it fat?
Every way to get rid of gyno on this page is aimed at glandular tissue. If what sits under the nipple is fat, none of it applies, can you get rid of gyno becomes the wrong question, and lean body composition is the whole answer. The distinction decides how to get rid of gyno, and the reviews put it in one line: gynecomastia is benign proliferation of glandular breast tissue in men, and breast cancer, which is far rarer, can usually be distinguished by careful examination (PMID 25112235).
| Finding | What it usually means | Read as |
|---|---|---|
| Soft, diffuse fullness that follows body fat and shrinks when you cut | Pseudogynecomastia: adipose tissue, not gland | Fat |
| Firm, rubbery disc directly under the areola, moves with the nipple | Glandular tissue, the definition of gynecomastia (PMID 25112235) | Gland |
| Tender, sore or itchy nipple with a small lump, weeks into a cycle | Early proliferative phase, the stage the SERM trials treated (PMID 10651345) | Gland, early |
| Painless, long-standing, unchanged for a year or more | Likely fibrotic; medical response unlikely (PMID 17881754) | Gland, late |
| One side only, hard, fixed, skin change or discharge | Outside the scope of this page; a clinician rules out other causes (PMID 25112235) | Clinician now |
Most lifters asking how to get rid of gyno have a mixture, gland under fat, and the two are managed separately: the fat by the deficit, the gland by the methods below. The hormone state that grew the gland is described on high estrogen symptoms on steroids, and the risk factors on gynecomastia risk on steroids.
How long does it take to get rid of gyno?
How long it takes to get rid of gyno is set by the tissue, not the method. The trials that reported how to get rid of gyno with a treatment course ran it for weeks to months, and the outcomes were measured at the end of that course.
| Stage | Duration in the study | What was measured | Outlook |
|---|---|---|---|
| Prevention, at the start of exposure | 48 weeks alongside an antiandrogen | Gynecomastia in 73 percent on placebo, 10 percent with tamoxifen, 51 percent with anastrozole (PMID 15681525) | Mostly prevented |
| Early, weeks to a few months | Median symptom duration 3 months | Complete resolution 78.2 percent on tamoxifen (PMID 10651345); 10 of 13 men responded to a 3-month course (PMID 15998589) | Reversible in most |
| Established, up to about 2 years | Mean duration 28.3 months, 3 to 9 month course | Nodule shrank 2.1 cm on tamoxifen and 2.5 cm on raloxifene; some improvement in 86 and 91 percent (PMID 15238910) | Reversible in many |
| Treated after symptoms began | Started a median 180 days after exposure | Tamoxifen still cut the frequency of gynecomastia, odds ratio 0.2 (PMID 15863377) | Partly reversible |
| Fibrotic, long-standing | No trial | Fibrous replacement of the gland; medical therapy not expected to work, surgery when it does not resolve (PMID 17881754, PMID 25112235) | Surgical |
Two things to take from the table about how to get rid of gyno. First, relapse is real, and it is the part of how to get rid of gyno that forums skip: in the Hong Kong series, five of the tamoxifen responders developed a recurrent breast mass (PMID 10651345), which is what happens when the estrogen state that grew the tissue is still there. Second, the prevention row is the strongest row, and it is the one steroid users skip: 73 percent to 10 percent is a bigger effect than any treatment figure on this page.
What the trials show for each way to get rid of gyno
Four drugs have human outcome data on how to get rid of gyno with medication: two selective estrogen receptor modulators, one antiandrogen and one aromatase inhibitor. The chart puts their measured results on how to get rid of gyno side by side; the rows come from different populations, so they are a map of what works, not a head-to-head race.
The estrogen receptor modulators carry the evidence on how to get rid of gyno without surgery. Tamoxifen produced complete resolution in 78.2 percent of adult men and raloxifene reduced adolescent nodules by more than half in 86 percent (PMID 10651345, PMID 15238910). In a 13-man series, 10 responded to a three-month course, one stopped for calf tenderness and no other adverse effects were reported (PMID 15998589). A review of tamoxifen safety in men found that fewer than 5 percent withdrew for toxicity and that adverse events were rarest in the infertility and idiopathic gynecomastia groups (PMID 27152880).
The prevention trials are the ones a steroid user asking how to get rid of gyno should read twice. In 114 prostate patients starting an antiandrogen that raises estradiol, gynecomastia developed in 73 percent on placebo, 10 percent with tamoxifen and 51 percent with anastrozole (PMID 15681525). In a second trial, 35 of 51 men on the antiandrogen alone developed gynecomastia or breast pain against 4 of 50 with tamoxifen, and when tamoxifen was started only after symptoms began, it still cut the frequency of gynecomastia with an odds ratio of 0.2 (PMID 15863377).
That is the closest measured model of how to get rid of gyno before a cycle grows it: estradiol goes up, the gland grows, and blocking the receptor stops it.
None of this is a protocol for how to get rid of gyno. These drugs are prescription medicines with their own risks, the doses in the trials were set for the populations studied, and the Dutch clinic that saw 180 users noted that self-treatment with aromatase inhibitors, clomiphene, hCG and tamoxifen was routine and unsupervised (PMID 29845939).
The point of the data is narrower: how to get rid of gyno with medication is a question with a measured answer, and the answer is a clinician and an estrogen receptor modulator, early. That is also the only measured answer to how to get rid of gyno without surgery. The hormone panel that shows whether the estrogen state is still active is on estradiol before steroids.
Why aromatase inhibitors are the wrong tool for existing gyno
The forum answer to how to get rid of gyno is an aromatase inhibitor, because the problem is estrogen. The trials say the reflex is the wrong answer to how to get rid of gyno once tissue exists. In 80 adolescents with pubertal gynecomastia, six months of anastrozole produced a 50 percent volume reduction in 38.5 percent against 31.4 percent on placebo, a difference that was not significant, even though the testosterone to estradiol ratio rose 166 percent (PMID 15356042).
In the prostate prevention trial, the same question of how to get rid of gyno before it forms was answered the same way: anastrozole left 51 percent with gynecomastia against 10 percent on tamoxifen, and it carried more adverse events, 69 percent against 35 (PMID 15681525).
The reason an inhibitor is not how to get rid of gyno is mechanical. An inhibitor lowers the estradiol in circulation; a receptor modulator, the measured answer to how to get rid of gyno, blocks the receptor in the breast itself, where the gland is listening. Lowering estradiol also has costs of its own that sit on other pages, the crashed estrogen state above all. For a lifter the practical conclusion is short: an inhibitor is a question about the whole cycle and the whole panel, not a way to get rid of gyno that is already there.
When surgery is the only way to get rid of gyno
Once the gland has been replaced by fibrous tissue, how to get rid of gyno has one answer, and the reviews are unanimous that surgery is the option when gynecomastia does not resolve spontaneously or with medical therapy (PMID 25112235). The useful data on surgery as the way to get rid of gyno are about which technique and what it costs.
A different dataset from the chart above: complication rates by surgical approach across 94 studies and 7,294 patients treated between 1987 and 2020. Innocenti 2022, PMID 35138423.
The authors concluded that, as a way of how to get rid of gyno surgically, combining excision with aspiration seems to reduce the complication rate compared with excision alone, with the caveat that classifications and techniques varied across the 94 papers.
Satisfaction after surgery to get rid of gyno is the other measurable. In 192 Danish patients treated for gynecomastia, those with a maximising decision style were younger, more often had gynecomastia following anabolic steroid use, and reported worse satisfaction with their nipples and worse psychological and social function after treatment (PMID 34704122). Read plainly: the steroid-user group asking how to get rid of gyno is the group most likely to be disappointed by a good operation, because the expectation is a chest that never had gyno rather than a chest that has been corrected.
Surgery removes the gland and is the definitive way to get rid of gyno; it does not change the hormone state that grew it. Anyone who has settled how to get rid of gyno with excision and is planning a further cycle is planning to test the surgeon's work against the same estradiol that made the first gland, which is why the risk page and the post cycle therapy page belong in the same conversation as the consultation.

Five mistakes that turn reversible gyno into a surgical case
Each of these is common in men asking how to get rid of gyno, and each moves tissue from the green rows of the timeline table toward the red one.
1. Waiting to see if it goes away. The early phase is the phase that responds, and the one in which how to get rid of gyno is still a medical question; the reviews describe the fibrotic phase as the one that does not (PMID 17881754). The adolescent data show the window is longer than twelve months for many (PMID 15238910), but nobody knows how long theirs is, and the reviews say treatment should be pursued early rather than waited out (PMID 25112235).
2. Treating it with an aromatase inhibitor. Anastrozole was no better than placebo on existing pubertal tissue (PMID 15356042) and far weaker than tamoxifen at prevention (PMID 15681525). It is the wrong tool for the question of how to get rid of gyno that is already there, and it is not how to get rid of gyno without surgery either.
3. Cutting body fat and calling it fixed. Fat responds to a deficit; gland does not, so can you get rid of gyno by dieting is a no. A firm disc under the areola after the cut is the same disc, now more visible (PMID 25112235). Getting lean is not how to get rid of gyno.
4. Stopping the medication and restarting the cause. Five of the tamoxifen responders in the Hong Kong series relapsed (PMID 10651345), which is how to get rid of gyno once and grow it back. Tissue grown by an estrogen state regrows in the same state, and whether you can get rid of gyno twice with the same drug is a question the series did not answer.
5. Self-treating from a forum. The Dutch clinic recorded routine unsupervised use of aromatase inhibitors, clomiphene, hCG and tamoxifen among 180 users (PMID 29845939). The drugs in this article are prescription medicines with their own adverse event profiles (PMID 27152880), and how to get rid of gyno is a diagnosis first and a prescription second.
Verdict: early tissue responds, old tissue needs a surgeon
How to get rid of gyno has two answers and one variable. When the gland is new, an estrogen receptor modulator under a clinician gave complete resolution in 78.2 percent of adult men (PMID 10651345) and improvement in 86 to 91 percent of adolescents (PMID 15238910), and used at the start of exposure it cut the incidence from 73 percent to 10 (PMID 15681525). When the gland is fibrous, surgery is the measured option, with a complication rate of about 12 percent for combined techniques and 31 percent for excision alone (PMID 35138423).
Can you get rid of gyno without surgery? In the early window, the data say usually. Can you get rid of gyno after that window? Only with a surgeon. The variable in how to get rid of gyno is time, and the only way to know where you are on it is an examination. Everything upstream of that examination, the estradiol, the compound, the panel, is on the PED side effects hub and on blood tests before steroids.
How to get rid of gyno: frequently asked questions
Can you get rid of gyno without surgery?
Often, if the tissue is recent. Tamoxifen produced complete resolution in 78.2 percent of 68 men with idiopathic gynecomastia of median three months duration (PMID 10651345), and raloxifene or tamoxifen improved 86 to 91 percent of adolescents whose gynecomastia had lasted a mean of 28 months (PMID 15238910). Once the gland has become fibrous, medical therapy is not expected to work and surgery is the option (PMID 17881754, PMID 25112235). A clinician decides which stage you are at.
How long does it take to get rid of gyno?
The trials measured outcomes after courses of three to nine months. A three-month course resolved painful gynecomastia in 10 of 13 men (PMID 15998589), and a 3 to 9 month course shrank adolescent nodules by 2.1 to 2.5 cm (PMID 15238910). Fibrotic tissue does not shrink on a timeline; it is removed.
Does gyno from steroids go away on its own after a cycle?
Sometimes, when it is caught in the first weeks and the estrogen state ends. Gynecomastia developed in 19 percent of 100 men during a cycle, and by one year the prevalence of side effects had returned to baseline in that cohort (PMID 33038020). Tissue that has been there for months is less likely to regress, and the risk of relapse is highest when another cycle recreates the same hormone state (PMID 10651345).
Will an aromatase inhibitor get rid of gyno?
The trials say no for tissue that already exists. Anastrozole gave a 50 percent volume reduction in 38.5 percent of adolescents against 31.4 percent on placebo, not a significant difference (PMID 15356042), and in a prevention trial it left 51 percent with gynecomastia against 10 percent on tamoxifen (PMID 15681525). The receptor modulator blocks the breast; the inhibitor only lowers circulating estradiol.
Is tamoxifen safe for men with gyno?
A review of randomised and non-randomised studies found fewer than 5 percent of men withdrew from tamoxifen for toxicity, with the fewest adverse events in the infertility and idiopathic gynecomastia groups; long-term data in men are lacking (PMID 27152880). In a 13-man series one patient stopped for calf tenderness (PMID 15998589). It is a prescription medicine and the decision belongs to a prescriber.
Will getting lean get rid of gyno?
It removes the fat component only. Gynecomastia is by definition glandular tissue (PMID 25112235), and a firm disc under the areola stays after a cut. Pseudogynecomastia, which is fat, does respond to a deficit, and most lifters have some of both.
Is gyno surgery worth it?
For fibrotic tissue it is the only measured fix. Across 7,294 patients, complications occurred in 11.76 percent of combined excision and aspiration cases against 30.64 percent for excision alone (PMID 35138423). Satisfaction was lower in younger patients and in those whose gynecomastia followed steroid use (PMID 34704122), so expectations matter as much as technique.
What is the fastest way to get rid of gyno?
Prevention, measured properly, beats every treatment figure: gynecomastia developed in 73 percent of men on an estradiol-raising drug with placebo and 10 percent with tamoxifen over 48 weeks (PMID 15681525). For tissue that already exists, the fastest measured route is early assessment and, if a clinician prescribes it, an estrogen receptor modulator while the gland is still proliferative (PMID 10651345). Nothing over the counter has trial data.
Sources and further reading
Every figure on this page comes from one of the thirteen papers below, each checked against its PubMed record on 27 September 2026. The Braunstein review has no abstract on PubMed and is cited for its clinical staging only. Reference links are dofollow to support open science.
Keep reading
Four pages upstream and downstream of how to get rid of gyno: who gets gyno and the first signs, the estrogen state behind it, the baseline number, and what happens when the cycle ends.
Final Educational Note
This article is educational and is not medical advice. It reports what clinical trials and reviews measured about how to get rid of gyno, including drugs that are prescription medicines with their own risks. It gives no dose, schedule or protocol, does not recommend any drug or surgical technique, and is not an encouragement to use anabolic steroids, which carry serious health and legal risks. More guides sit on the PED side effects hub.
A lump, pain or change in the male breast is a clinical finding that a physician should examine, both to stage the tissue and to rule out the rarer causes. Read more about how this site works on the about page and in the full disclaimer.


