Testosterone Steroids

IS TESTOSTERONE A STEROID? YES, THE ORIGINAL ONE
Testosterone is the parent anabolic steroid. Every other compound is a modified copy. What separates a medical treatment from a steroid cycle is not the molecule, it is the dose.
This guide covers the testosterone steroids family: esters and forms, replacement vs athlete doses, muscle, estradiol, side effects by form, heart safety and recovery. The ester guides are enanthate, cypionate and propionate.
Testosterone steroids in three numbers
Three figures show where medicine ends and testosterone steroids use begins.
Upper end of the treated range in a 5,246 man trial (PMID 37326322).
Lowest level between weekly shots (PMID 11701431).
At replacement doses, over about 33 months (PMID 37326322).
Study figures come from PubMed papers. What athletes do in practice is not studied; where we describe it, we say so.
What this testosterone steroids guide covers
Is testosterone a steroid, and how its esters and forms differ.
Replacement vs supraphysiological doses: muscle, estradiol, blood, lipids, heart.
Fertility, recovery and stacks athletes report, next to studied doses.
Not coveredA protocol. Nothing here is a dose to take. Practice figures describe what people do, with personal and unstudied risk.
Women and transgender care. Doses and risks there are different.
Is testosterone a steroid?
Yes. Testosterone is a steroid hormone and the original anabolic androgenic steroid. Synthetic steroids are modified versions of it, so all testosterone steroids share its core actions (PMID 36644692).
It works by binding the androgen receptor. It can also turn into DHT, a stronger androgen, or into estradiol, an estrogen (PMID 36644692).
The testosterone vs steroids question is really a dose question. Doctors treat low testosterone back to the normal range. Steroid users take it far above that range (PMID 37326322, 11701431).
It is the base of most real cycles. In a Dutch clinic for steroid users, testosterone was the most common drug (PMID 29845939).
Testosterone steroids: forms and esters
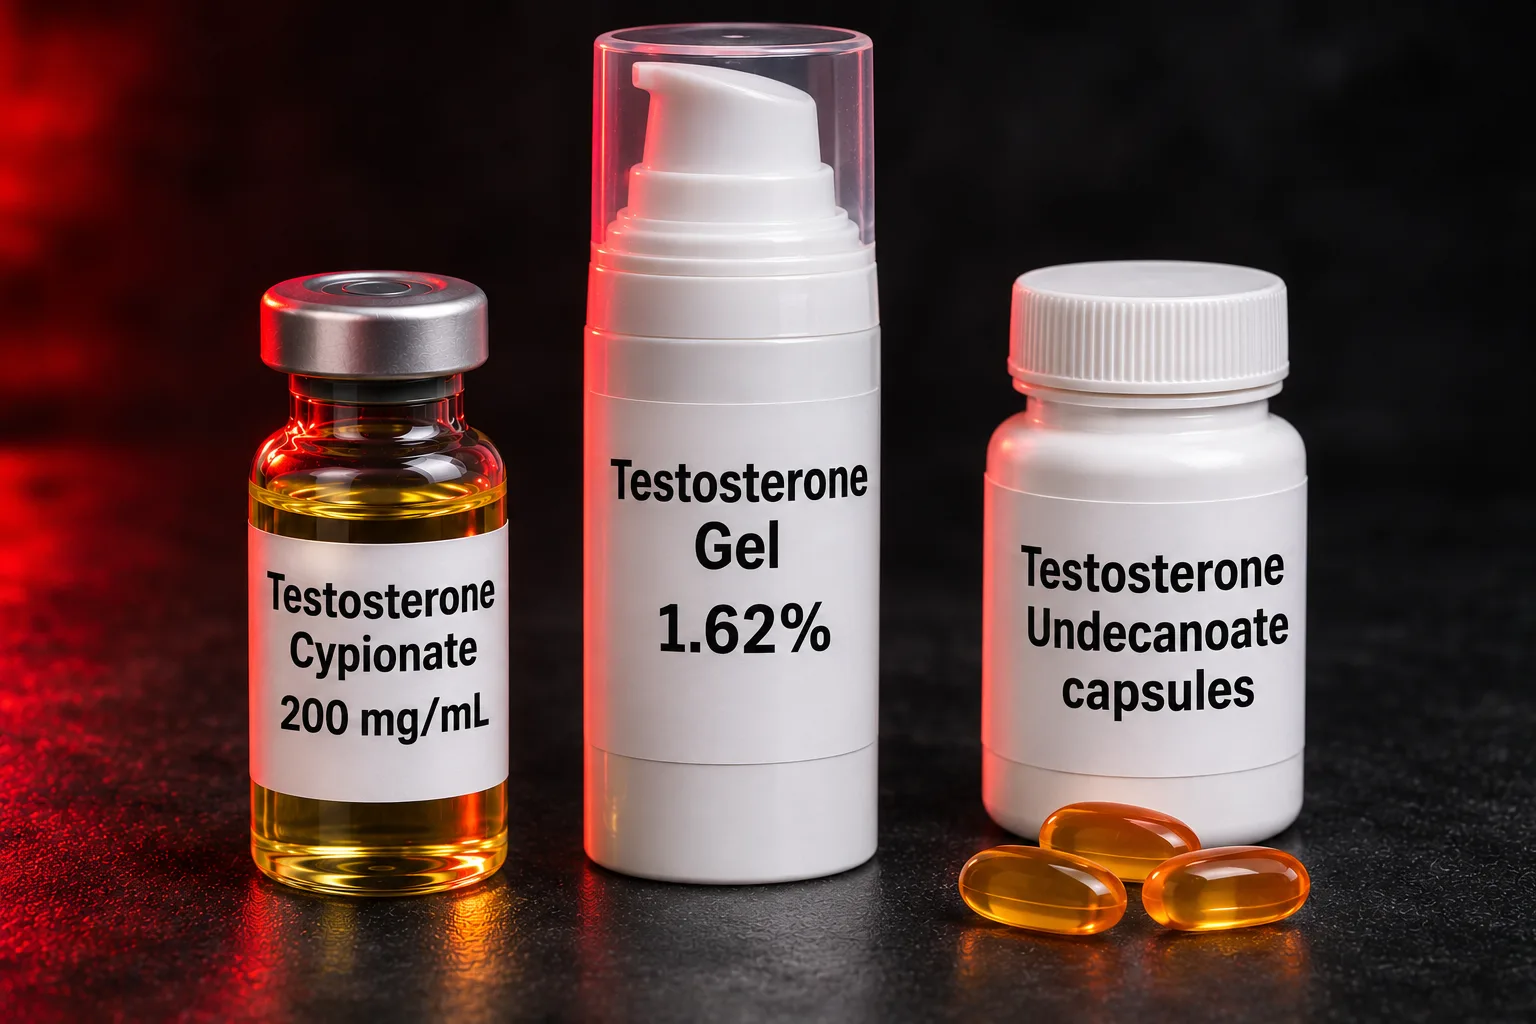
In all testosterone steroids the hormone is the same. What changes is how it gets in and how fast it leaves.
Plain testosterone lasts about 10 minutes after injection. The propionate ester stretches that to about 1 day and enanthate to about 4.2 days (PMID 36644692).
Swallowed testosterone mostly dies in the liver. Of 25 mg, less than 1 mg reaches the blood; even the undecanoate ester only reaches 6.8 percent (PMID 36644692).
A newer oral undecanoate capsule fixed much of that. 87 percent of men reached normal levels, but systolic blood pressure rose 3 to 5 mm Hg (PMID 32382745).
| Form | How it behaves | Source |
|---|---|---|
| Propionate injection | Half life about 1 day | PMID 36644692 |
| Enanthate injection | Half life about 4.2 days; peaks after shots | PMID 36644692, 10522982 |
| Cypionate injection | Pooled with enanthate in trials | PMID 34445892 |
| Oral undecanoate | 87% normal levels; BP +3 to 5 mm Hg | PMID 32382745 |
| Gel | Daily; used in the large safety trials | PMID 37326322, 26886521 |
Testosterone steroids: replacement vs a cycle
In the largest safety trial, men started below 300 ng/dL and were treated to 350 to 750 ng/dL (PMID 37326322).
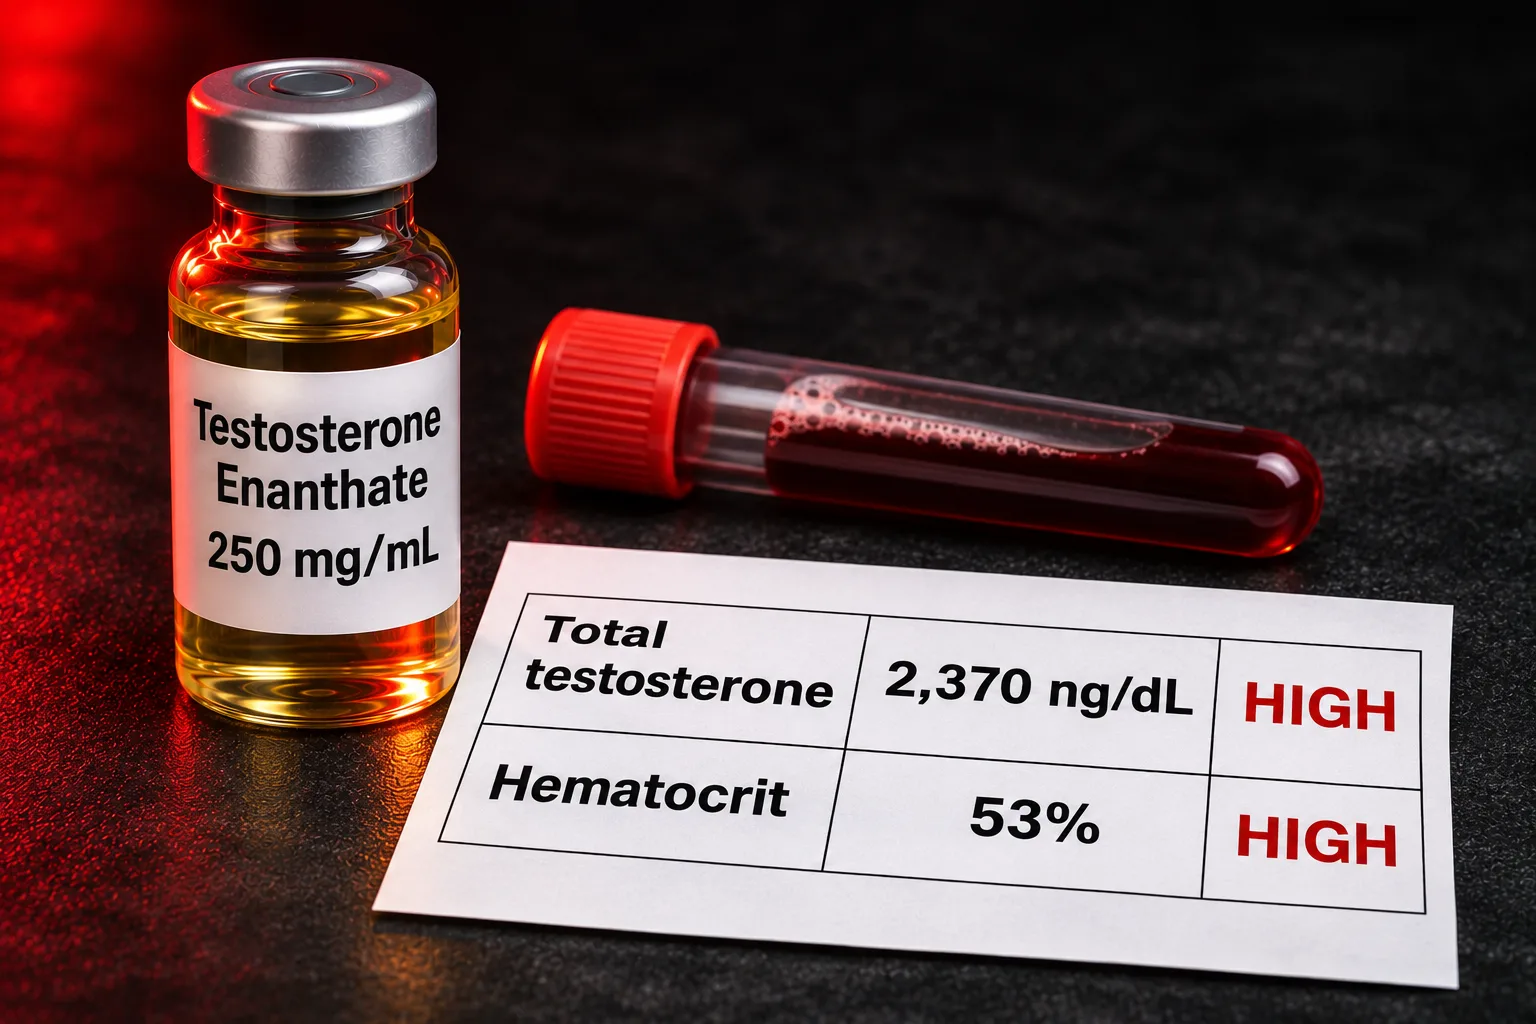
Athlete level doses go far past that. With natural production off, 300 mg a week gave a trough of 1,345 ng/dL and 600 mg gave 2,370 ng/dL (PMID 11701431).
Replacement brings modest benefits. In 790 men over 65, gel raised sexual activity, desire and erections over placebo. Energy did not improve (PMID 26886521).
What testosterone steroids do to muscle
With testosterone steroids, muscle follows dose. In 61 young men over 20 weeks, fat free mass rose 3.4 kg at 125 mg a week. It rose 5.2 kg at 300 mg and 7.9 kg at 600 mg (PMID 11701431).
Older men respond the same. Men aged 60 to 75 gained 4.2, 5.6 and 7.3 kg at the same three doses (PMID 15562020).
With lifting, 600 mg a week added 6.1 kg of fat free mass in 10 weeks. Bench press rose 22 kg and squat 38 kg (PMID 8637535).
Low levels cost muscle. When men were dropped to very low testosterone, lean mass and thigh muscle fell, and leg press strength fell on placebo (PMID 24024838).
Testosterone steroids and estradiol
Part of testosterone becomes estradiol through aromatase (PMID 36644692). That estradiol does real work in men.
A trial of 400 men blocked their own hormones, then gave testosterone with or without an aromatase blocker (PMID 24024838).
Low testosterone drove the loss of muscle and strength. Low estradiol drove the gain in body fat. Both lowered sexual function (PMID 24024838).
On injections, estradiol runs high for several days after each shot (PMID 10522982).
Testosterone steroids side effects by form and dose
Every form raised hematocrit in a network meta analysis of 29 trials. Oral undecanoate and enanthate or cypionate injections raised it most (PMID 34445892).
Thicker blood
Rises with dose, more in older men (PMID 18160461); 43.8% abnormal hematocrit on shots vs 15.4% on a patch (PMID 10522982).
HDL at high dose
Unchanged up to 300 mg a week; down 8 mg/dL at 600 mg (PMID 11788637).
Mood in a minority
At 600 mg a week, 84% had minimal change; 4% became markedly hypomanic (PMID 10665615).
Blood pressure on oral
Systolic up 3 to 5 mm Hg on oral undecanoate (PMID 32382745).
Testosterone steroids and the heart
At replacement doses the best evidence is reassuring. TRAVERSE gave 5,246 men aged 45 to 80 with heart risk either gel or placebo (PMID 37326322).
Heart attack, stroke or cardiovascular death hit 7.0 percent on testosterone and 7.3 percent on placebo, over a mean 33 months (PMID 37326322).
It was not free of risk. Atrial fibrillation, acute kidney injury and pulmonary embolism were more common on testosterone (PMID 37326322).
That trial kept levels at 350 to 750 ng/dL. It says nothing about levels of 1,345 to 2,370 ng/dL (PMID 37326322, 11701431).
Fertility and recovery after testosterone steroids
Testosterone switches off sperm production. In a WHO trial, 200 mg a week made 157 of 271 men azoospermic, on average after 120 days (PMID 1977002).
After stopping, sperm took a median 3.7 months to reach 20 million per mL, and 6.7 months to return to baseline (PMID 1977002).
After real cycles, recovery is less sure. Of 641 men who had stopped steroids, 48.2 percent had normal LH, FSH and testosterone (PMID 38102386).
Testosterone steroids in cycles and stacks: studied vs practice
This section describes practice, not advice. Doses athletes report are not studied in healthy people beyond 600 mg a week. Using them is a personal, unstudied risk, and every body responds differently.
In a Dutch clinic, cycles had a median of three drugs for a median 10 weeks, and testosterone was the most used (PMID 29845939).
Users commonly describe 250 to 500 mg a week as a first cycle base. That is practice, not a studied protocol.
| Stack | Why athletes use it | What the evidence says |
|---|---|---|
| Test + Deca | Classic bulk | Common pairing in clinic users (PMID 29845939) |
| Test + trenbolone | Hard mass or recomp | Common in clinic users; no trial (PMID 29845939) |
| Test + Dianabol | Fast start to a bulk | No trial of this pair; see the Dianabol guide |
| Test + Anavar | Cutting phase | No trial of this pair; see the Anavar guide |
| Test + Winstrol | Cutting, show prep | No trial of this pair; see the Winstrol guide |
Bloodwork for testosterone steroids
| Marker | What moved | Guide |
|---|---|---|
| Total testosterone | 300 to 750 ng/dL on TRT; 1,345 to 2,370 on 300 to 600 mg a week (PMID 37326322, 11701431) | Suppression |
| Hematocrit | +1.4 to +4.3 points by form (PMID 34445892) | CBC markers |
| Estradiol | Above normal for days after shots (PMID 10522982) | Estradiol |
| HDL | −8 mg/dL at 600 mg only (PMID 11788637) | Lipid panel |
| LH, FSH | Normal in 48.2% after stopping (PMID 38102386) | 7 markers |
7 proven facts about testosterone steroids
1. Testosterone is a steroid. The parent of all AAS (PMID 36644692).
2. Esters set the timing. About 1 day for propionate, 4.2 for enanthate (PMID 36644692).
3. Muscle follows dose. +3.4 to +7.9 kg at 125 to 600 mg a week (PMID 11701431).
4. Estradiol keeps fat off. Low estradiol drove fat gain in men (PMID 24024838).
5. Every form raises hematocrit. +1.4 to +4.3 points (PMID 34445892).
6. TRT did not raise heart attacks. 7.0% vs 7.3% (PMID 37326322).
7. It switches off sperm. Median 3.7 months to recover (PMID 1977002).
Testosterone steroids: frequently asked questions
Is testosterone a steroid?
Yes. It is a steroid hormone and the original anabolic androgenic steroid; synthetic AAS are modified versions of it (PMID 36644692).
Testosterone vs steroids: what is the difference?
Mostly dose. TRT keeps levels around 350 to 750 ng/dL (PMID 37326322); 600 mg a week gave troughs of 2,370 ng/dL (PMID 11701431).
Which testosterone ester is best?
They release the same hormone. Propionate lasts about 1 day and enanthate about 4.2 days (PMID 36644692); trials pool enanthate and cypionate (PMID 34445892).
Is testosterone replacement bad for the heart?
In TRAVERSE, major heart events were 7.0% vs 7.3% on placebo, but atrial fibrillation, kidney injury and pulmonary embolism were more common (PMID 37326322).
What are the main testosterone side effects?
Higher hematocrit with every form (PMID 34445892) and estradiol peaks after shots (PMID 10522982). Also lower HDL at 600 mg (PMID 11788637) and lower sperm counts (PMID 1977002).
Does oral testosterone work?
Plain oral testosterone barely reaches the blood (PMID 36644692). A newer oral undecanoate got 87% of men to normal levels (PMID 32382745).
Should estradiol be blocked on testosterone?
Not to zero. In men, low estradiol increased body fat and lowered sexual function (PMID 24024838).
How long does fertility take to recover?
After 200 mg a week, sperm reached 20 million per mL in a median 3.7 months (PMID 1977002).
Sources and further reading
Every study figure on this page comes from one of the 16 papers below, checked against PubMed on 1 November 2026. Practice figures are marked as practice. Reference links are dofollow to support open science.
More from the steroids series
Four guides that sit closest to this one.
Final Educational Note
This article is educational and is not medical advice. It reports what trials and reviews say about testosterone. Practice doses are described, not recommended, and carry personal, unstudied risk.
Chest pain, an irregular heartbeat, one sided leg swelling or sudden shortness of breath need a doctor. More guides sit on the steroids hub. Read more on the about page and in the full disclaimer.


