Recovery and Fatigue in Training

MUSCLE RECOVERY AND FATIGUE: 7 PROVEN FACTS AND THE SIGNS OF OVERTRAINING
Muscle recovery is the window between two sessions in which a trained muscle rebuilds more than it lost, and it has a measured length. After 3 sets to failure, young men performed fewer reps than baseline at 24 hours, matched it at 48 hours and beat it at 72 hours; men aged 50 to 65 were still behind at 72 to 96 hours (PMID 12741861).
Muscle protein synthesis after one session is 112 percent above resting at 3 hours and still 34 percent at 48 hours (PMID 9252485). The signs of overtraining are harder to pin down: the ECSS and ACSM consensus found no marker that meets the criteria for diagnosis (PMID 23247672), and in resistance training the only reliable indicator is a sustained drop in performance (PMID 31820373).
This guide reads the muscle recovery evidence rather than the recovery industry: what fatigue is and how fast each part of it clears, how long does it take for muscles to recover by age and volume, what soreness does and does not mean, the signs of overtraining and the three stages behind them, what HRV and blood markers can and cannot tell you, what one night of sleep loss costs, which recovery methods were measured to help and which were measured to blunt growth, and what deloads actually do. Every figure comes from a PubMed abstract listed at the end. The series lives on the training hub.
Muscle recovery in brief
Three numbers frame muscle recovery: how long a hard session takes to clear, what one bad night costs, and how much a common painkiller takes off the result.
Performance was below baseline at 24 hours in every group, back to baseline at 48 hours, and above it at 72 hours in the young 3-set group, 11.2 against 10.2 reps; men aged 50 to 65 were still behind the young at 72 hours and close to it at 96 (PMID 12741861). Protein synthesis after one bout was still 34 percent above resting at 48 hours (PMID 9252485).
Sleep loss cut performance by 7.56 percent on average, by about 0.4 percent for every hour awake before the task, with evening tasks hit and morning tasks largely spared (PMID 35708888). One night without sleep lowered muscle protein synthesis 18 percent and testosterone 24 percent in 13 young adults (PMID 33400856).
Young adults taking the maximal over-the-counter ibuprofen dose grew their quadriceps 3.7 percent against 7.5 percent on low-dose aspirin, a 34 cubic centimetre difference, with smaller strength gains on the flywheel leg (PMID 28834248). Cold water immersion after training cut type II fibre growth by about 17 percent in a separate trial (PMID 26174323).
Every figure on this page about muscle recovery is taken from a PubMed abstract listed at the end. Where a marker is proposed but not validated, the page says so. Where lifters describe their muscle recovery on forums, including on anabolic steroids, it is reported as a description, not as evidence.
What this muscle recovery guide covers
Fatigue and its timeline: central and peripheral fatigue, how long does it take for muscles to recover after a session by age and volume, soreness, damage and the repeated bout effect.
Signs of overtraining: functional overreaching, nonfunctional overreaching and overtraining syndrome as the consensus defines them, what HRV, creatine kinase and performance tests can and cannot detect.
What changes muscle recovery: sleep, massage, stretching, cold water, anti-inflammatory drugs, antioxidants, alcohol, protein, creatine and deloads, each as measured, plus what men on anabolic steroids describe against what was measured.
Not coveredHow many sets to recover from. The dose side is on training volume explained; the growth side on what builds muscle.
Product reviews. Supplements marketed for recovery are on recovery supplements; daily protein targets on protein intake explained.
Injury. A pulled or torn muscle is a clinical problem, not a muscle recovery problem, and is not covered here.
What fatigue is: the two places muscle recovery has to happen
Fatigue is a reduced capacity to produce voluntary force that outlasts the session, and it comes from two places. Peripheral fatigue is impaired function in the muscle itself; central fatigue is a reduced capacity of the nervous system to drive the muscle (PMID 27932676).
The two recover on different clocks, which is the first fact about muscle recovery. After brief, high-intensity work, central fatigue is largely gone within about 2 minutes and the excitation-contraction and blood-flow components of peripheral fatigue within 3 to 5 minutes, but impaired calcium release or sensitivity inside the fibre can keep force down for hours (PMID 27932676). After long, low-intensity work the order flips: force returns partly within minutes as the central component recovers, yet voluntary activation may not be back within 30 minutes and peripheral fatigue is still incomplete at 20 to 30 minutes (PMID 27932676).
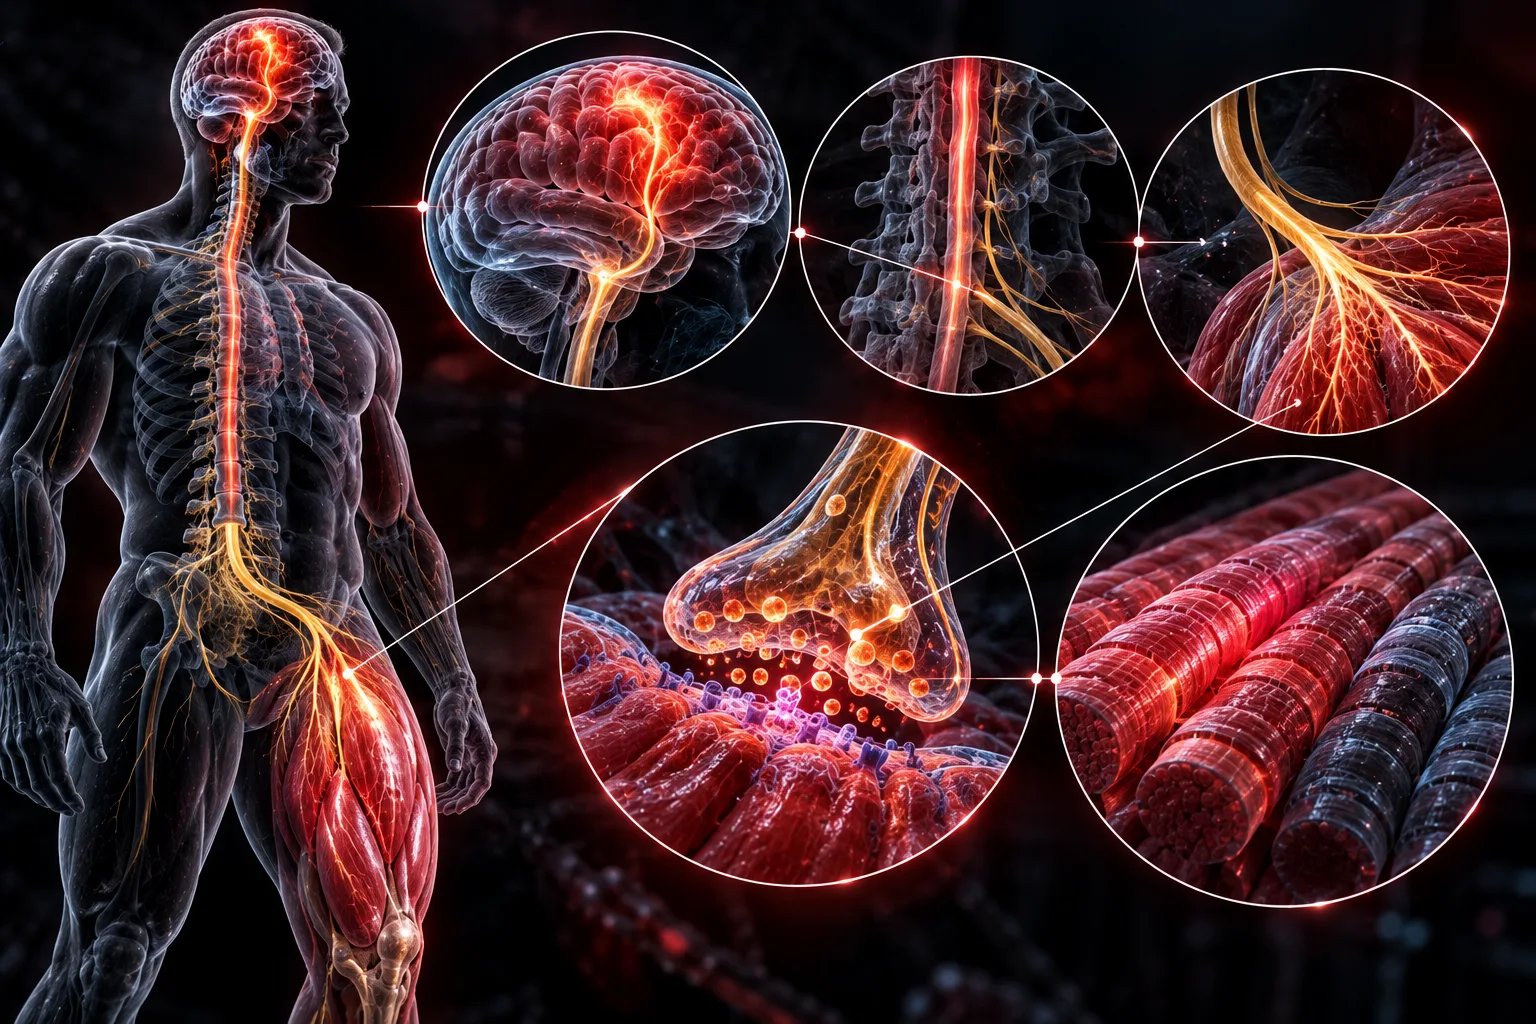
That is the within-session picture of muscle recovery. What those minutes mean for your sets is on how long to rest between sets. Muscle recovery between sessions is a different and slower process, and it is the one this page is about: the muscle replaces the protein it broke down, repairs the structural damage of unaccustomed work, and in the trained state does both with less and less damage each time (PMID 27782911). The mechanism that turns that repair into growth, protein synthesis staying above resting for two days (PMID 9252485), is covered on what builds muscle; here the question is how long it takes and what interferes with it.
| Component | What was measured | Read as |
|---|---|---|
| Central fatigue, brief hard work | Reduced capacity to voluntarily activate the muscle; recovers typically within 2 minutes after brief high-intensity exercise (PMID 27932676) | Gone between sets |
| Peripheral fatigue, fast part | Excitation-contraction coupling and reperfusion of the muscle; recovers within 3 to 5 minutes (PMID 27932676) | Rest intervals handle it |
| Peripheral fatigue, slow part | Prolonged impairment of intracellular calcium release or sensitivity; complete recovery may take some hours (PMID 27932676) | Why the second session of the day is weaker |
| Central fatigue, long work | After long low-intensity exercise voluntary activation may not recover within 30 minutes (PMID 27932676) | Why conditioning before lifting costs reps |
| Muscle damage and repair | Reps to failure below baseline at 24 hours, back at 48, above at 72 in young men (PMID 12741861); damage highest after the first session of a programme and attenuated by week 3 (PMID 27219125) | Muscle recovery proper: 48 to 72 hours |
How long does it take for muscles to recover: 24, 48, 72 and 96 hours
How long does it take for muscles to recover after a hard session? The cleanest answer comes from a study that simply retested. Thirty men did 3 or 7 sets to failure and were retested at 24, 48, 72 and 96 hours. In all three groups, performance was significantly below baseline at 24 hours and not different from baseline at 48 hours.
In men aged 18 to 30 who had done 3 sets, repetitions at 72 hours were higher than in the first session, 11.2 against 10.2, a supercompensation that the 7-set group only approached at 96 hours. Men aged 50 to 65 after 3 sets were performing below the young at 72 hours, 9.9 against 11.2 reps, with the gap still close to significant at 96 hours (PMID 12741861).

Two details of that trial matter for muscle recovery in practice. Variability between people was large at every time point, so the group means are a map, not a schedule (PMID 12741861). And 7 sets did not take measurably longer to recover from than 3 in young men; the main difference was that the supercompensation came later (PMID 12741861). Protein synthesis fits the same window: 112 percent above resting at 3 hours, 65 percent at 24 hours and 34 percent at 48 hours after one bout, with breakdown back to resting by 48 hours (PMID 9252485).
How long does it take for muscles to recover, then, depends more on age than on set count within the range the trials used: roughly 48 hours to baseline for young men, 72 hours for a measurable gain, and longer for men over 50 (PMID 12741861). The frequency side of that, how often a muscle can be trained once it has recovered, is on training volume explained; the split templates that space sessions 48 to 72 hours apart are on 3 day workout split and full body dumbbell workout.
Soreness and damage: what they say about muscle recovery and what they do not
Soreness is the signal most lifters use, and it is the least informative one on this page.
Delayed onset muscle soreness peaks a day or two after unaccustomed work, is worst after eccentric actions, and is most common at the start of a season or when a new exercise is introduced (PMID 12617692). Six mechanisms have been proposed, from lactic acid to connective tissue damage to inflammation, and the review concludes that a combination of two or more is likely; the practical consequences are reduced range of motion, reduced peak torque and altered recruitment that can load tendons and ligaments in unfamiliar ways (PMID 12617692).
Soreness is also a poor guide to muscle recovery. In the 10-week biopsy study, muscle damage was highest after the first session and unrelated to how much the muscle eventually grew; only the protein synthesis measured once damage had faded, at weeks 3 and 10, correlated with growth (PMID 27219125). The second exposure to the same work produces far less damage, the repeated bout effect, through neural adaptation, changes in the mechanical properties of the muscle, remodelling of the extracellular matrix and biochemical signalling (PMID 27782911). A lifter who is sore every week is doing something new every week, not recovering badly.
What the DOMS review recommends for muscle recovery is modest: reduce intensity and duration for 1 to 2 days after a session that produced heavy soreness, train less affected muscles meanwhile, and introduce eccentric or novel work progressively over 1 to 2 weeks (PMID 12617692).
Exercise itself is the most effective relief, though the analgesic effect is temporary (PMID 12617692). Creatine kinase in blood tracks damage but has athlete-specific reference intervals of 82 to 1,083 U/L in men, twice the upper limit of moderately active non-athletes and up to six times that of inactive people, so a high value in a lifter is often normal for a lifter (PMID 17526622). The bloodwork side is on why is my CK high.
Signs of overtraining: functional overreaching, nonfunctional overreaching and the syndrome
The signs of overtraining are easier to list than to validate, and most lists confuse them with ordinary muscle recovery. The joint consensus statement of the European College of Sport Science and the American College of Sports Medicine describes a continuum: functional overreaching, a short-term performance decrement that leads to improvement after recovery; nonfunctional overreaching, which occurs when the balance between training and recovery is not respected and brings no later gain; and overtraining syndrome, defined by prolonged maladaptation of the athlete and of several biological, neurochemical and hormonal mechanisms (PMID 23247672).
The distinction between the last two is very difficult, depends on the clinical outcome and on excluding other causes, and the athletes often show the same clinical, hormonal and other signs (PMID 23247672).

The consensus is explicit about markers. Fatigue, performance decline and mood disturbance are thought to be more severe in the syndrome than in nonfunctional overreaching, but there is no scientific evidence to confirm or refute that; hormones, performance tests, psychological tests and biochemical and immune markers are all in use, and none of them meets all the criteria for general acceptance (PMID 23247672). Diagnosis works by exclusion: organic disease, infection, caloric restriction, insufficient carbohydrate or protein, iron or magnesium deficiency and allergies are ruled out first (PMID 23247672).

For lifters specifically the evidence on signs of overtraining is thinner still. A systematic review of 22 studies that tried to induce overreaching or overtraining with resistance exercise found that eight produced a performance decrement with follow-up, four produced a decrement without follow-up, and ten produced no decline at all; a lack of standardised follow-up testing and diagnostic criteria prevents consistent determination of any of the three states, and no marker other than a sustained decrease in performance has been established (PMID 31820373). The review notes that overtraining may be related to frequent high-intensity and monotonous resistance training (PMID 31820373).
| Sign | Evidence | Read as |
|---|---|---|
| Sustained performance decrease | The one indicator established in resistance training (PMID 31820373); the consensus defines all three stages by the duration of the performance decrement and whether it rebounds (PMID 23247672) | The sign of overtraining that counts |
| Mood disturbance, fatigue | Thought more severe in the syndrome than in nonfunctional overreaching; no evidence to confirm or refute (PMID 23247672) | Part of the picture, not a test |
| Hormones, immune and biochemical markers | In use, but none meets all criteria for accepted diagnosis (PMID 23247672) | Rule out disease, do not diagnose |
| Resting heart rate variability | Resting RMSSD rose with positive adaptation (SMD 0.58) and also rose with overreaching (SMD 0.26); the direction does not distinguish them (PMID 26888648) | Cannot tell good from bad |
| Post-exercise heart rate recovery and HRV | Increased with both positive adaptation and overreaching (PMID 26888648) | Same problem |
| Heart rate acceleration | Increased with positive adaptation in one study and decreased with overreaching (SMD minus 0.48); a potential indicator, not an established one (PMID 26888648) | Promising, single study |
| Creatine kinase | Athlete reference range 82 to 1,083 U/L, sport-specific, twice non-athlete limits (PMID 17526622) | Tracks damage, not overtraining |
The practical reading for muscle recovery is that functional overreaching is normal and productive, a hard block followed by a rebound (PMID 23247672); the sign to act on is a performance decline that lasts past the planned rest, and the response to it is more recovery and the exclusion of illness and under-eating, not another supplement (PMID 23247672). How a block is structured so that the dip is planned is on progressive overload explained.
Monitoring muscle recovery: HRV, blood markers and the only test that works
Monitoring muscle recovery is meant to show whether an athlete is adapting and to catch nonfunctional overreaching, illness and injury early; the review of monitoring tools finds that very few markers have strong scientific support and that no single definitive marker exists (PMID 25200666). The tools in use include external load, perceived effort, heart rate, lactate, training impulse, heart rate recovery, neuromuscular tests, biochemical and hormonal panels, questionnaires and sleep, and the review stresses individualisation over any one number (PMID 25200666).
Heart rate variability is the marker lifters now carry on their wrists, and the meta-analysis that pooled 24 studies in endurance athletes is sobering. Positive adaptation raised resting RMSSD with a standardised difference of 0.58 and post-exercise RMSSD by 0.60; overreaching that reduced performance also raised resting RMSSD, by 0.26, and post-exercise RMSSD by 0.64 (PMID 26888648). The authors conclude that increases in vagal indices occur with both positive and negative adaptation, so additional measures are required to tell which is which, and that heart rate acceleration, which fell with overreaching, may be a potential indicator (PMID 26888648). A rising HRV is not proof of muscle recovery.
What does work for tracking muscle recovery is the test the overtraining literature keeps returning to: performance, tracked over time against a planned expectation (PMID 31820373, PMID 25200666). The 24-to-96-hour study used repetitions to failure at a fixed load and could separate young from old and recovered from not (PMID 12741861). Dissociation between external load and internal load, the same session feeling harder, is the signal the monitoring review points to (PMID 25200666). For the blood side, the markers that matter and their lifter-specific ranges are on the bloodwork hub.
Sleep: the muscle recovery variable with the largest measured effect
Sleep is the one muscle recovery input with a measured dose-response in both directions. Across 69 publications and 227 outcomes, sleep of 6 hours or less cut exercise performance by 7.56 percent on average, in every category from anaerobic power to strength to skill; the loss was about 0.4 percent for every hour awake before the task, consistent after total deprivation and after a late-restricted night, and concentrated in tasks performed in the evening, with morning tasks largely unaffected (PMID 35708888).
At the tissue level, one night of total sleep deprivation in 13 young adults reduced postprandial muscle protein synthesis by 18 percent, raised cortisol 21 percent and lowered testosterone 24 percent, with no change in protein degradation markers (PMID 33400856).

The other direction has been measured too. Eleven college basketball players who extended sleep by 111 minutes a night for 5 to 7 weeks cut their timed sprint from 16.2 to 15.5 seconds, raised free-throw accuracy 9 percent and three-point accuracy 9.2 percent, and improved reaction time, sleepiness and fatigue scores (PMID 21731144).
The broader review of sleep and muscle recovery finds the effects of sleep loss equivocal for some maximal efforts and consistent for sport-specific tasks, and notes that reduced sleep can produce an autonomic imbalance that mimics the overtraining syndrome and raise pro-inflammatory cytokines (PMID 25315456). The mechanistic hypothesis, that sleep debt shifts muscle toward a proteolytic state through cortisol up and testosterone and IGF-1 down, is published as a hypothesis (PMID 21550729) and matches the measured hormone changes (PMID 33400856).

The practical reading is the one the meta-analysis gives: if a short night is unavoidable, avoid total deprivation and late restriction, and train in the morning rather than the evening (PMID 35708888). The hormonal side of sleep on TRT is on TRT and sleep.
What helps muscle recovery and what measurably blunts it
Ninety-nine studies of muscle recovery techniques were pooled in 2018. Active recovery, massage, compression garments, immersion, contrast water and cryotherapy all reduced delayed onset soreness, with effects from small to large; massage was the most powerful technique for both soreness and perceived fatigue, and massage and cold exposure reduced inflammatory markers most, with creatine kinase down by a standardised 0.37 and interleukin-6 and C-reactive protein by about 0.36 to 0.38 (PMID 29755363).
Stretching did not make the muscle recovery list: the Cochrane review of 12 studies found pre-exercise stretching reduced soreness by half a point and post-exercise stretching by one point on a 100-point scale, and even the one large field trial of 2,377 people found a 4-point reduction the authors call very small (PMID 21735398).
Feeling better and muscle recovery are not the same measurement, and three common habits show the gap. Cold water immersion after each session for 12 weeks produced smaller gains in strength and muscle mass than active recovery; the active group increased type II fibre area 17 percent and myonuclei per fibre 26 percent, the cold group did not, and in a separate acute study cold water blunted satellite cell activity and the kinase signalling that regulates growth (PMID 26174323). A 7-week trial found the same: cold water attenuated type II fibre hypertrophy and the mTORC1 signal while leg press strength improved equally (PMID 31513450).

| Method | Evidence | Read as |
|---|---|---|
| Sleep | Loss: minus 7.56 percent performance, minus 18 percent synthesis (PMID 35708888, PMID 33400856); extension: faster sprint, better accuracy (PMID 21731144) | The largest lever |
| Massage | Most effective technique for soreness and perceived fatigue across 99 studies; reduces CK and inflammatory markers (PMID 29755363) | Feel better; growth not measured |
| Active recovery, compression | Small to large reductions in soreness and perceived fatigue (PMID 29755363); exercise is the most effective temporary relief for DOMS (PMID 12617692) | Reasonable, symptom-level |
| Stretching | Half a point to one point on a 100-point soreness scale; not clinically important (PMID 21735398) | Does nothing for soreness |
| Cold water immersion | Reduces soreness (PMID 29755363) but blunted type II fibre growth, myonuclear addition and satellite cell activity over 12 weeks (PMID 26174323) and over 7 weeks (PMID 31513450) | Avoid after hypertrophy sessions |
| High-dose ibuprofen | 1,200 mg a day for 8 weeks: quadriceps growth 3.7 percent against 7.5 percent on 75 mg aspirin, smaller strength gains (PMID 28834248) | Halves the result |
| Vitamin C and E | 1,000 mg vitamin C and 235 mg vitamin E daily for 11 weeks blocked the rise in mitochondrial markers COX4 and PGC-1 alpha with endurance training, without changing VO2max (PMID 24492839) | Blunts cellular adaptation |
| Alcohol after training | 1.5 g/kg, about 12 standard drinks, cut myofibrillar synthesis 24 percent even with 25 g of protein and 37 percent with carbohydrate (PMID 24533082) | Suppresses the anabolic response |
| Protein supplement | No consistent acute effect on soreness or damage markers; benefits appear when taken after daily training sessions and in energy deficit (PMID 24435468) | Daily total matters, timing less |
| Creatine | After eccentric damage, isokinetic strength 10 percent and isometric 21 percent higher during recovery, CK 84 percent lower at 48 hours to 7 days, in 14 untrained men (PMID 19490606) | Faster force recovery after damage |
The pattern across the table is that the methods which reduce soreness fastest act on inflammation, and inflammation is part of how muscle recovery becomes growth: the cold water, ibuprofen and antioxidant trials all blunted the signalling they suppressed (PMID 26174323, PMID 28834248, PMID 24492839). Massage and active recovery reduce symptoms without a measured cost (PMID 29755363); the costs are measured for the methods that go deeper. The supplement side is on recovery supplements and creatine loading phase.
Deloads, breaks and maintenance: planned muscle recovery
A deload is planned muscle recovery, a reduction in training to let accumulated fatigue clear, and the trials that tested it find that it costs less than lifters fear. Thirty-nine trained men and women did a 9-week high-volume programme either continuously or with one full week off at the midpoint: lower-body muscle size, local endurance and power did not differ between groups, while the continuous group gained more isometric and dynamic strength and reported slightly better readiness to train (PMID 38274324). A week off did not cost muscle; it cost a little strength.
Longer breaks from training behave the same way for muscle recovery over longer horizons. Fourteen men trained the bench press for 24 weeks either continuously or in three cycles of 6 weeks on and 3 weeks off; chest and triceps size and strength were the same at the end, and the periodic group regrew faster in each retraining cycle than the continuous group, whose rate had slowed (PMID 23053130).
After a 16-week build, young adults who cut to one third or one ninth of their weekly dose kept the fibre size they had built for 32 weeks, with the one-third dose adding more, while adults aged 60 to 75 did not hold size at either reduced dose (PMID 21131862). Progressing volume within a block and then cutting it back is also measured: adding 4 or 6 lower-body sets every 2 weeks for 12 weeks gave more squat strength than constant volume, with a possible small size benefit that plateaued at the top (PMID 37796222).
Proximity to failure is the other lever on muscle recovery cost. Across 15 studies, sets to true momentary failure gave no hypertrophy advantage over stopping short, effect size 0.12, and any definition of set failure only a trivial edge of 0.19 (PMID 36334240). Grinding the last rep buys little growth and spends recovery. How the weekly dose is set so that a deload is rarely needed is on training volume explained; what the training stimulus does when calories fall is on cutting vs bulking training.
Muscle recovery on anabolic steroids: what men describe and what was measured
What men describe. On forums, enhanced lifters describe muscle recovery that natural lifters do not: recovering from sessions that would have flattened them when natural, training a muscle again within a day or two without loss, tolerating twice the weekly sets, sleeping less and still progressing, and feeling the recovery advantage disappear within weeks of a cycle ending (forum posts). They also describe joint and tendon pain arriving before muscular fatigue does, and a crash in recovery and mood after the cycle (forum posts).
What is measured. No trial on this page measured recovery time, repetitions to failure at 24 to 96 hours, or any marker of fatigue in men on anabolic steroids, so the muscle recovery advantage that is described has not been quantified. What was measured is that 600 mg of testosterone enanthate a week for 10 weeks built muscle without training and built more with it, 6.1 kg of fat-free mass and 1,174 square millimetres of quadriceps area with a three-day programme (PMID 8637535).
A drug that raises protein synthesis at a fixed training dose would be expected to shorten the net-balance window after each session, but that expectation is not a measurement. The practical result lifters describe, more sessions absorbed per week, is consistent with the measured growth effect and remains undocumented in randomised data.
Nothing here is a protocol. The pharmacology is on what are anabolic steroids and the steroids hub; what the described post-cycle crash looks like in the hormonal data is on post-cycle therapy and hormonal recovery after steroids.
What lifters describe about muscle recovery that no trial has measured
The gym vocabulary of muscle recovery is older than the trials and some of it has been tested. Nothing in this section is evidence; it is a record of what lifters report, set against what has been measured.
What lifters describe. Soreness as the sign a muscle is not recovered; ice baths as recovery; stretching to prevent soreness; a high resting heart rate or low HRV as the signal to take a day off; a protein shake within 30 minutes as the recovery window; feeling overtrained after a hard week; and the belief that a deload sets you back (forum posts).
What is measured. Soreness peaks when it predicts nothing about growth (PMID 27219125) and performance returns before and after soreness on different schedules (PMID 12741861). Ice baths reduce soreness and blunt fibre growth (PMID 29755363, PMID 26174323). Stretching changes soreness by about one point in a hundred (PMID 21735398). HRV rises with good and bad adaptation alike (PMID 26888648).
What is measured, continued. Protein timing has no consistent acute effect on recovery; the daily total does (PMID 24435468). Feeling overtrained after a hard week is functional overreaching if performance rebounds, and the consensus has no marker to call it anything else (PMID 23247672). A week off did not cost muscle (PMID 38274324). The sensation of being recovered is not measured by any trial on this page; repetitions at a fixed load are.
Five muscle recovery mistakes the trials expose
Each comes from treating a feeling as a measurement of muscle recovery.
1. Icing the growth away. Cold water after sessions reduced soreness and cut type II fibre growth and myonuclear addition over 12 weeks (PMID 26174323); the 7-week trial found the same with strength spared (PMID 31513450).
2. Taking painkillers to train more. Maximal over-the-counter ibuprofen for 8 weeks produced 3.7 percent quadriceps growth against 7.5 percent on low-dose aspirin (PMID 28834248).
3. Reading HRV as a muscle recovery score. Resting and post-exercise HRV rose with positive adaptation and with overreaching (PMID 26888648). It cannot tell you which you are in.
4. Treating soreness as the muscle recovery clock. Reps to failure were back to baseline at 48 hours and above it at 72 in young men regardless of how they felt (PMID 12741861); damage was highest when it meant least (PMID 27219125).
5. Fixing recovery with everything except sleep. One short night cut performance 7.56 percent and synthesis 18 percent (PMID 35708888, PMID 33400856); no massage, supplement or deload on this page moves muscle recovery that much.
Verdict: muscle recovery is a 48 to 72 hour clock, read by performance
Read from the retest studies, the consensus statements and the intervention trials rather than from any gadget, muscle recovery works like this. Central and fast peripheral fatigue clear in minutes (PMID 27932676); the muscle itself is back to baseline at about 48 hours and above it at 72 in young men, later in older men (PMID 12741861), with protein synthesis elevated for two days after each session (PMID 9252485). Soreness and damage are loudest when they predict least (PMID 27219125). The signs of overtraining reduce, in the evidence, to one: a drop in performance that lasts longer than the planned rest, after illness and under-eating have been excluded (PMID 23247672, PMID 31820373).
Sleep is the muscle recovery input with the largest measured effect in both directions (PMID 35708888, PMID 33400856, PMID 21731144). Massage and active recovery ease symptoms without a measured cost (PMID 29755363); cold water, high-dose anti-inflammatories, antioxidant megadoses and alcohol ease symptoms or nothing at all and blunt the adaptation (PMID 26174323, PMID 28834248, PMID 24492839, PMID 24533082). A planned week off costs a little strength and no muscle (PMID 38274324). The signs of overtraining worth acting on are the ones that outlast that week.
For readers here the practical reading is that how long does it take for muscles to recover has an answer, and that muscle recovery has a method: two to three days for the muscle and minutes for the nervous system, and that the way to know is to retest, not to feel. Sleep more than you supplement, keep the cold and the ibuprofen for injuries, treat a hard week that rebounds as the plan working, and treat a slide that does not rebound as the one sign that counts. The dose side is on training volume explained, the growth side on what builds muscle, the loading side on progressive overload explained; the hub is training hub.
Muscle recovery: frequently asked questions
How long does it take for muscles to recover after a workout?
How long does it take for muscles to recover is about 48 hours to baseline and 72 hours to a measurable gain in young men. After 3 or 7 sets to failure, repetitions were below baseline at 24 hours, equal at 48, and higher at 72 in men aged 18 to 30 after 3 sets, 11.2 against 10.2; men aged 50 to 65 were still behind at 72 to 96 hours (PMID 12741861). Protein synthesis stays elevated for about two days, 112 percent above resting at 3 hours and 34 percent at 48 (PMID 9252485). Variability between people was large at every time point.
What are the signs of overtraining?
Among all the signs of overtraining, the only one established in resistance training is a sustained decrease in performance (PMID 31820373). The ECSS and ACSM consensus describes functional overreaching, which rebounds after rest, nonfunctional overreaching, which does not, and overtraining syndrome, a prolonged maladaptation; fatigue, mood disturbance and hormonal changes accompany all three, and no hormone, blood or psychological marker meets the criteria for diagnosis (PMID 23247672). Diagnosis works by excluding illness, under-eating and deficiencies first.
Is soreness a sign of good muscle recovery or bad?
Neither; soreness is a poor guide to muscle recovery. Soreness peaks a day or two after unaccustomed or eccentric work and is most common at the start of a programme (PMID 12617692). Muscle damage was highest after the first session of a 10-week programme and unrelated to how much the muscle grew; growth tracked the protein synthesis measured once damage had faded (PMID 27219125). The second exposure to the same work produces far less damage, the repeated bout effect (PMID 27782911). Performance returned to baseline at 48 hours whether or not soreness had (PMID 12741861).
Does HRV tell you when you are recovered?
Not reliably; HRV is not a muscle recovery score. Across 24 studies in endurance athletes, resting HRV rose with positive adaptation, SMD 0.58, and also rose with overreaching that reduced performance, SMD 0.26; post-exercise HRV and heart rate recovery increased in both cases too, so the authors conclude that additional measures are needed to tell good from bad adaptation (PMID 26888648). Heart rate acceleration fell with overreaching in a single study and is a potential indicator. Performance against expectation remains the test (PMID 25200666).
Do ice baths help muscle recovery?
They reduce soreness and blunt growth, so for muscle recovery they trade a feeling for a result. Cold water immersion reduced delayed onset soreness across the 99-study meta-analysis (PMID 29755363), but after each session for 12 weeks it produced smaller gains in strength and muscle mass than active recovery; the active group increased type II fibre area 17 percent and myonuclei per fibre 26 percent and the cold group did not (PMID 26174323). A 7-week trial found cold water blunted fibre hypertrophy and mTORC1 signalling while strength improved equally (PMID 31513450).
How much does sleep affect muscle recovery?
More than any other input measured on this page. Six hours or less cut exercise performance 7.56 percent on average across 69 studies, about 0.4 percent per hour awake before the task, with evening tasks hit hardest (PMID 35708888). One night without sleep lowered muscle protein synthesis 18 percent and testosterone 24 percent and raised cortisol 21 percent (PMID 33400856). Sleeping 111 minutes longer for 5 to 7 weeks cut a basketball sprint from 16.2 to 15.5 seconds and raised shooting accuracy about 9 percent (PMID 21731144).
Do painkillers slow muscle recovery?
High doses of anti-inflammatories blunt the adaptation. Young adults taking 1,200 mg of ibuprofen a day for 8 weeks grew their quadriceps 3.7 percent against 7.5 percent on 75 mg of aspirin, with smaller strength gains in the flywheel-trained leg (PMID 28834248). Daily vitamin C and E megadoses blocked the mitochondrial adaptation to endurance training (PMID 24492839), and alcohol after training cut protein synthesis 24 percent even with protein (PMID 24533082). The inflammation these habits suppress is part of how muscle recovery becomes growth.
Does a deload week set you back?
Not in muscle; a deload is planned muscle recovery. In 39 trained lifters, a full week off at the midpoint of a 9-week high-volume programme produced the same lower-body size, endurance and power as training straight through, with a smaller strength gain (PMID 38274324). Over 24 weeks, 3 weeks off after every 6 weeks of bench training matched continuous training for size and strength (PMID 23053130), and young adults kept trained fibre size for 32 weeks on one ninth of the dose (PMID 21131862).
Sources and further reading
Every figure on this page about muscle recovery comes from one of the 31 papers below, each checked against its PubMed abstract on 6 October 2026. One paper is a published hypothesis and is labelled as such in the text. Forum descriptions are reported as descriptions and carry no reference number. Reference links are dofollow to support open science.
Keep reading
Four pages from the training series: how many sets you are recovering from, what the recovery is building, how to load it, and what happens when a tendon rather than a muscle is the thing that hurts.
Final Educational Note
This article is educational and is not medical or coaching advice. It reports what trials, meta-analyses and consensus statements say about muscle recovery, fatigue and overtraining, and it reports how some lifters describe their own recovery, including on anabolic steroids, as a description of practice, not as guidance. Drug and supplement doses appear only as the trials used them; the page gives no programme or protocol, does not recommend any drug, and is not an encouragement to use performance-enhancing drugs, which carry serious health and legal risks. More guides sit on the training hub.
A performance decline that lasts for weeks despite rest, persistent fatigue with disturbed sleep or mood, resting heart rate changes, repeated illness, dark urine or severe muscle pain after training are reasons to consult a physician; several medical conditions produce the same picture as overtraining and are excluded first. Individual recovery varies widely. Read more about how this site works on the about page and in the full disclaimer.


